The ESMO Congress 2026 is the annual meeting of the European Society for Medical Oncology. It stands as one of the world’s most influential oncology platforms for presenting pioneering cancer research. The event takes place from October 23 to 27, 2026, in Madrid, Spain, at the IFEMA MADRID convention center, utilizing a highly accessible hybrid (in-person and virtual) format.
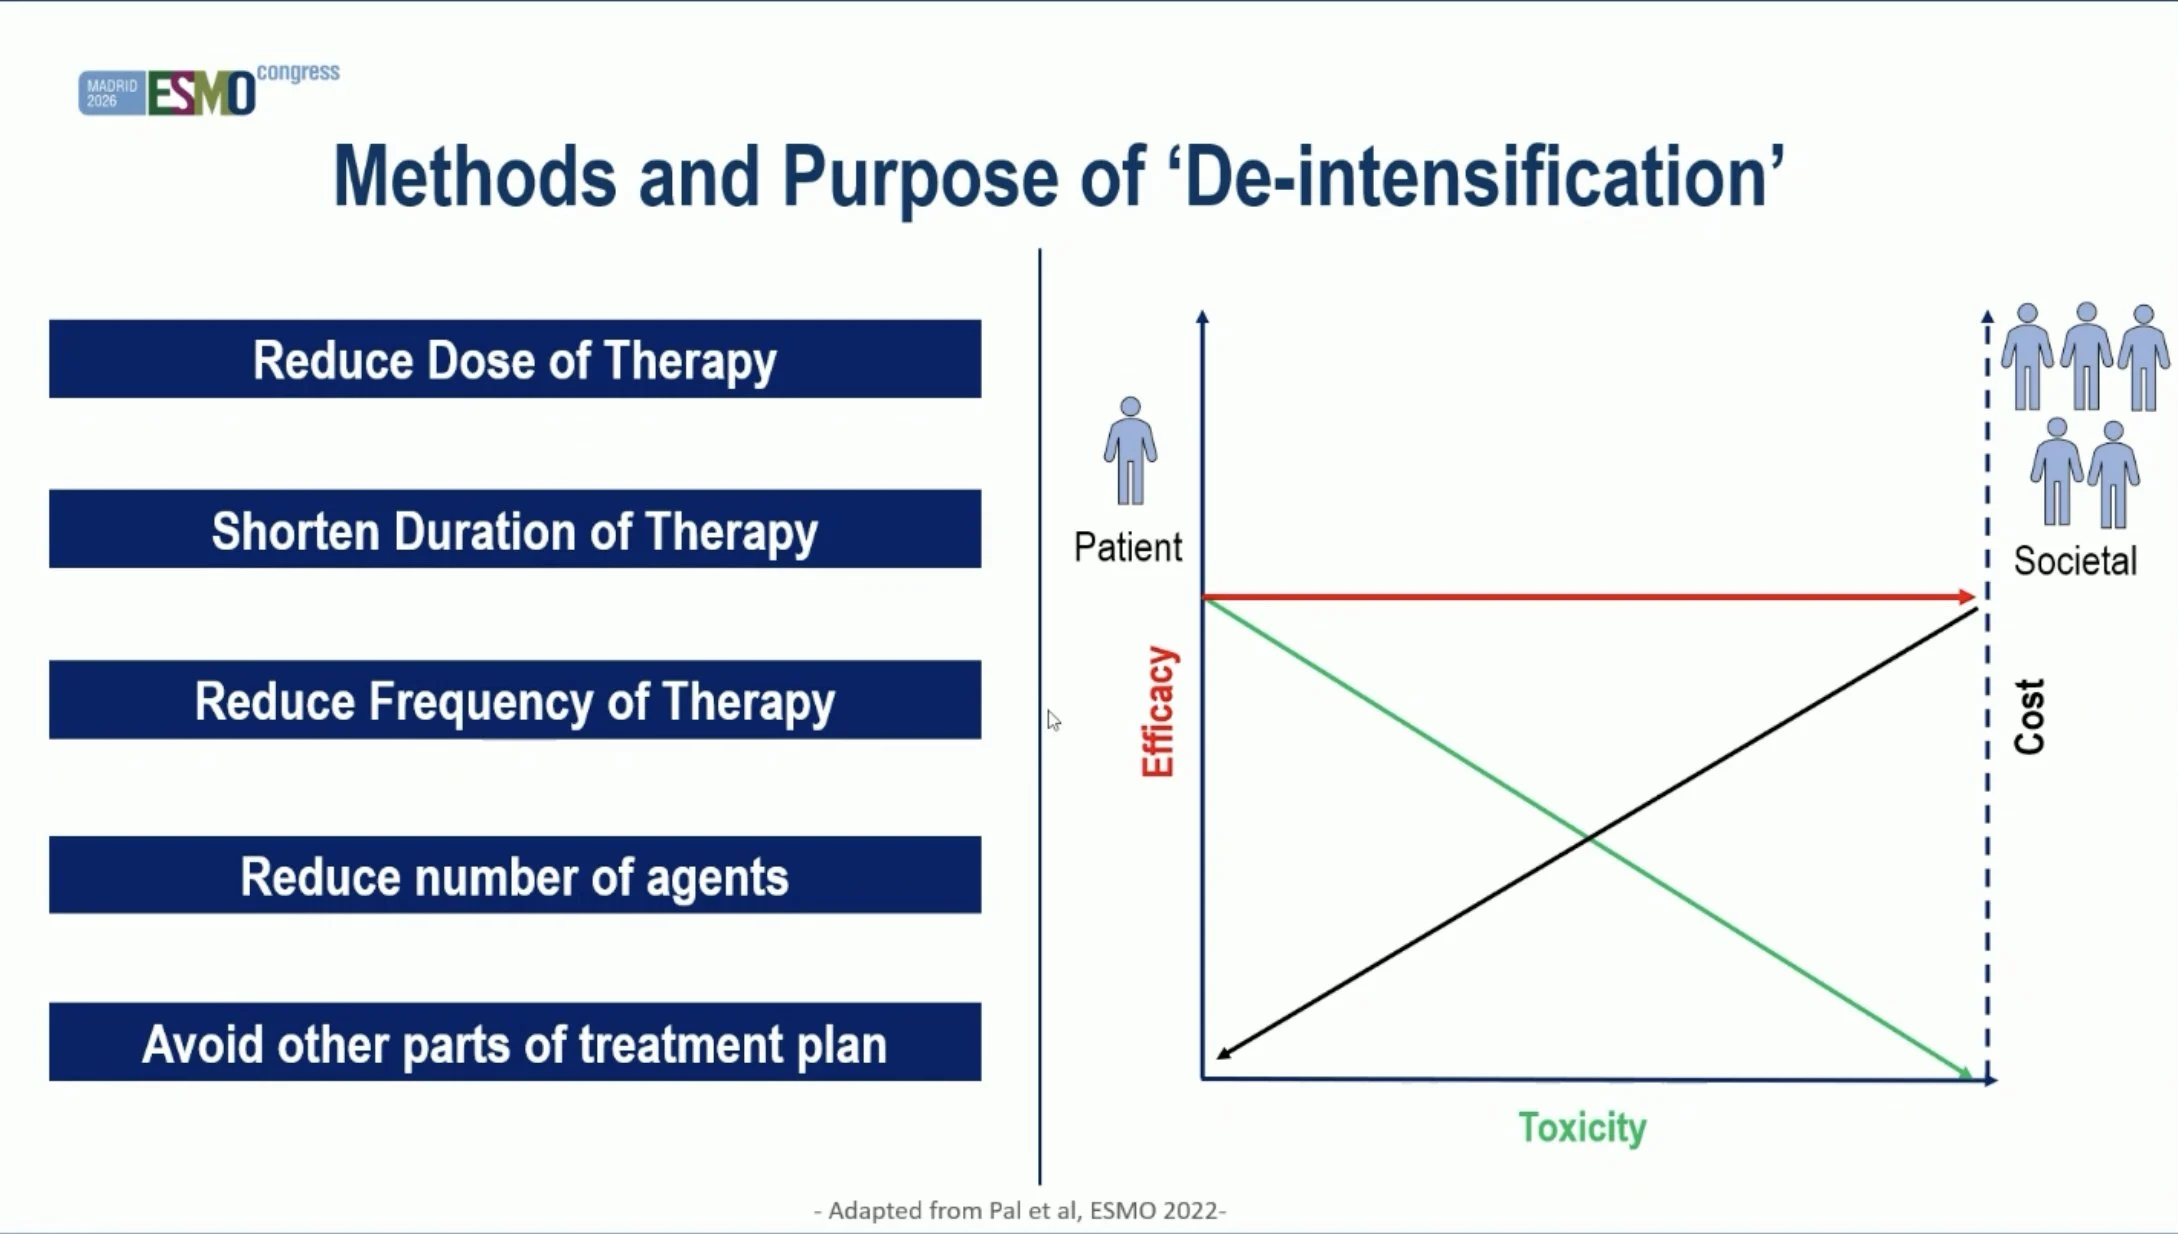
Stephen Liu, Chief, Division of Hematology and Oncology at Georgetown Lombardi Comprehensive Cancer Center, shared on X:
“Dr. Jarushka Naidoo with a fantastic discussion on de-escalation trials in oncology. A call out on why de-escalation studies are important and their limitations. And for MOIO in particular – lessons on trial design, non-inferiority, and pragmatism. A must-listen to all involved in trial design.
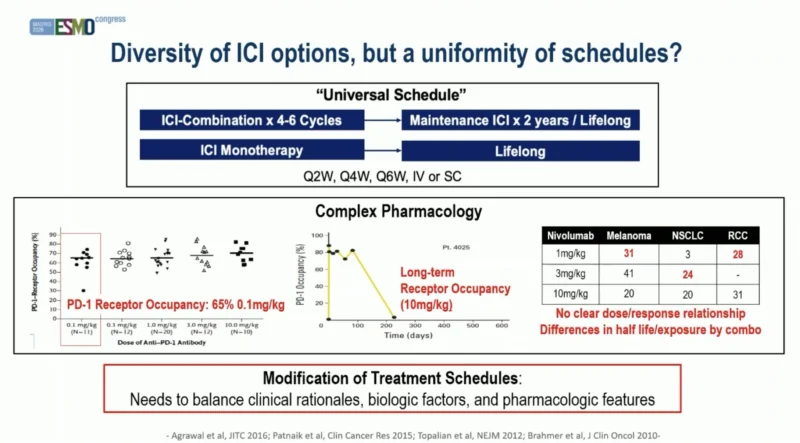
One of my favorite discussant. Dr Jordi Remon discusses early stage immunotherapy abstracts. Many options in the neoadjuvant and perioperative space, summarized beautifully. What is the value of adjuvant immunotherapy? Is receipt of adjuvant therapy a surrogate for fitness?
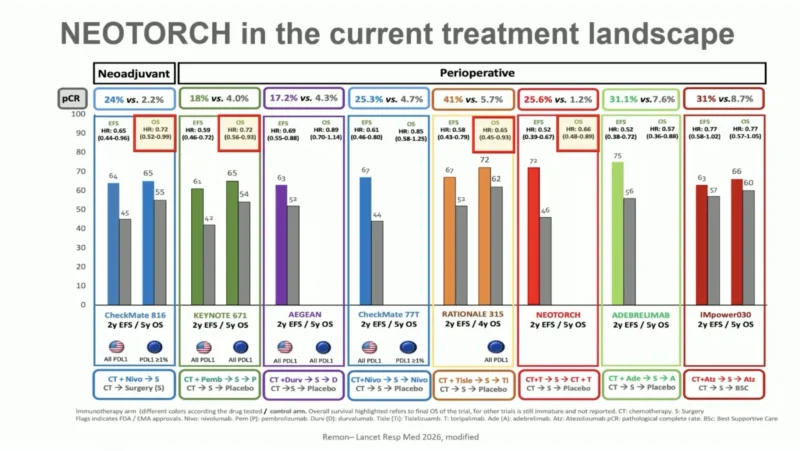 Some very important points brought up by Dr. Jordi Remon on the real value of adjuvant immunotherapy for resected NSCLC. What is the value of improving DFS without OS benefit? Neoadjuvant approach much clearer but perhaps we need to develop smarter. Happy Birthday to Dr. Remon!
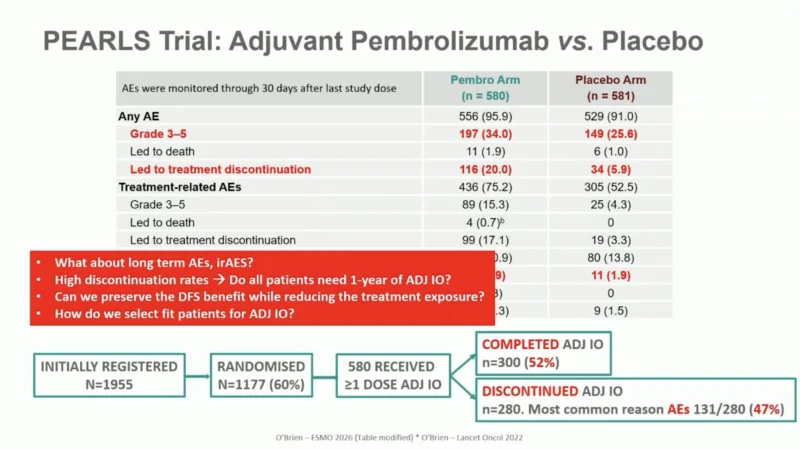
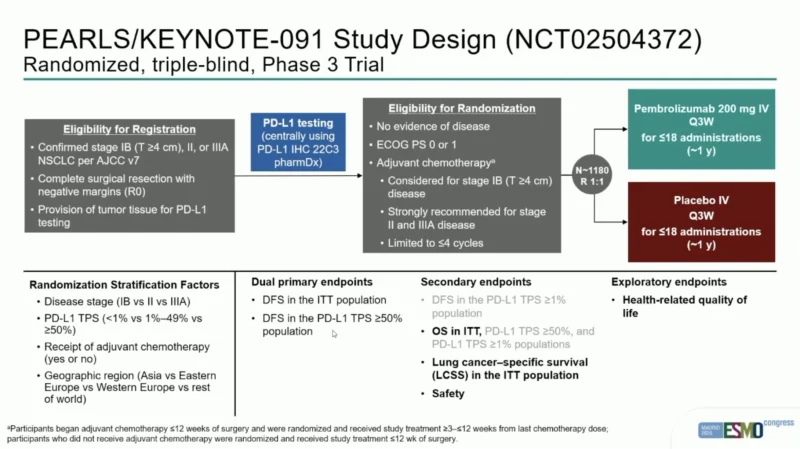
Dr. Mary O’Brien presents final analysis of phase III PEARLS/KEYNOTE-091 trial: adjuvant pembrolizumab for resected NSCLC with 87m f/u. In pts who received adjuvant chemo, DFS 58.7 vs 39.1m (HR 0.80) and no difference in survival: OS HR 0.91 with 6y DFS 69% vs 65%. In that group, improved lung cancer specific survival (HR 0.69, 6y rate 82% vs 75%).
Important longer follow up from DeLLphi-304 (2L tarlatamab vs SCLC) presented by Dr. Charlie Rudin at ESMO26 simultaneously published in Annals of Oncology. Median PFS 4.2 vs 3.2m, mOS 13.6 vs 8.4m, 2y OS 30% vs 15%, RR 35% vs 20%.
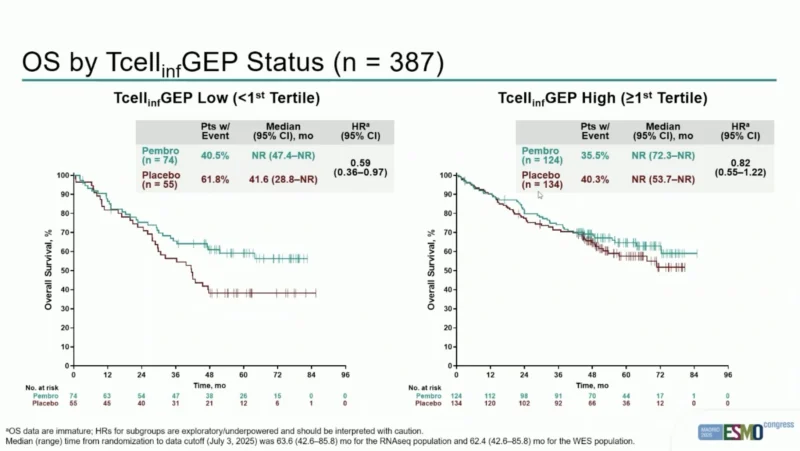
The brilliant Dr. Marina Garassino with biomarker analysis from the phase III KEYNOTE 671 study of perioperative pembrolizumab for resectable NSCLC showing association of T-cell inflamed gene expression profile and TMB with efficacy. Benefit across subgroups; inflamed profile associated with better prognosis.
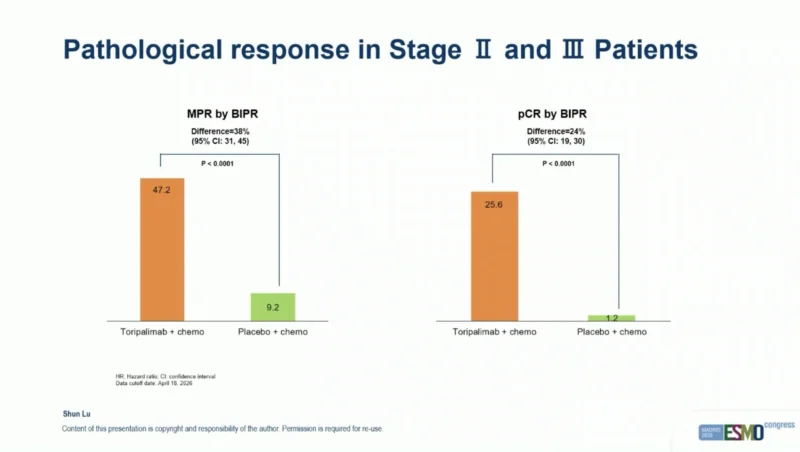
Dr. Shun Lu gives us the final analysis of the phase III Neotorch trial: perioperative toripalimab + chemotherapy for resectable stage II/III NSCLC. With 48.2m follow up, EFS 0.52 (median NR vs 20), MPR 47% vs 9%, pCR 26% vs 1%, OS HR 0.66.
Dr. Roberto Ferrara explains next-generation immune toxicities seen with next-generation immunotherapies. Rational design of SCORPION vs CRAB antibodies is a good example of intentional design to address toxicities. Very helpful overview.
 Dr. Tom Newsom-Davis shows some of the clinical data of bispecifics, trispecifics, and T-cell engagers. Why bispecifics targeting PD(L)1 and VEGF can be upgrades. Why T-cell engagers can disrupt cancers in unique ways.
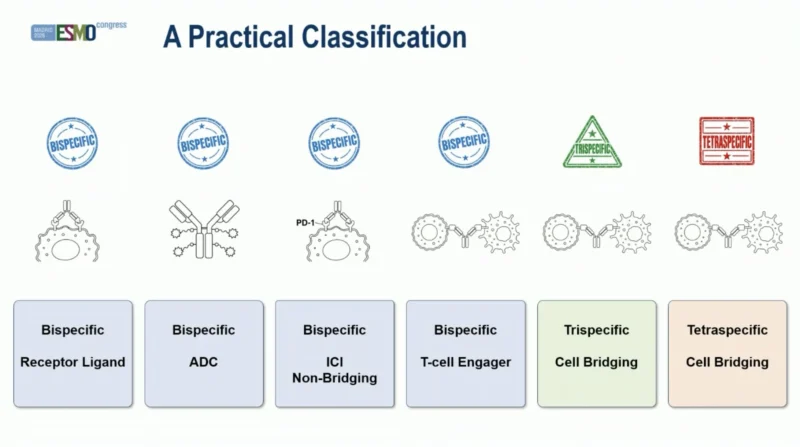
Highly recommend watching Dr. Tina Cascone in this lung education session for a mechanistic view of novel immunotherapy agents. Clear explanation of how function follows structure, the science behind bispecifics and trispecifics – combinatorial vs obligate. Watch online – tremendous resource for anyone involved in the space.
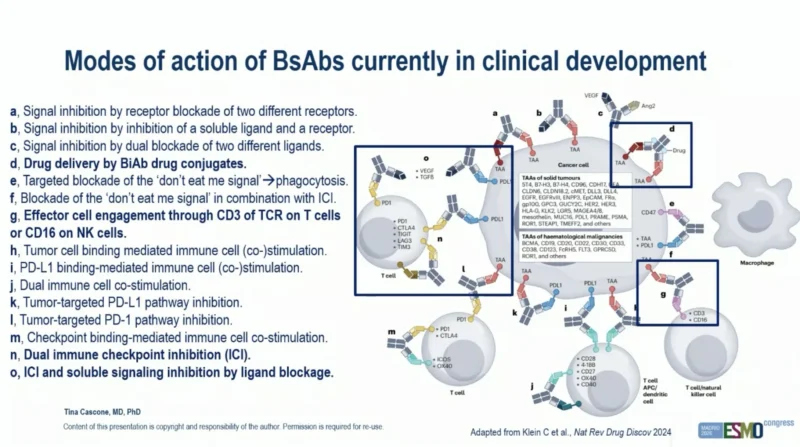
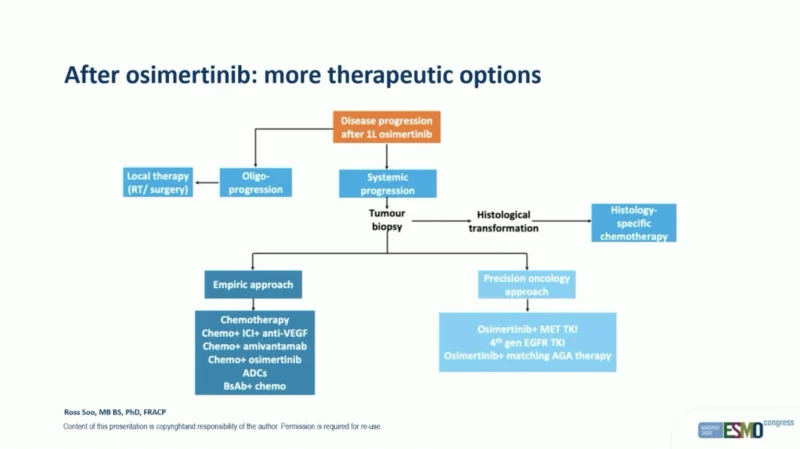
Dr. Ross Soo provides an overview of targeted therapy for oncogene+ NSCLC. A breakdown of things to consider for combination therapy. Escalation strategies including potential for ctDNA. How to approach progression: empiric vs precision.
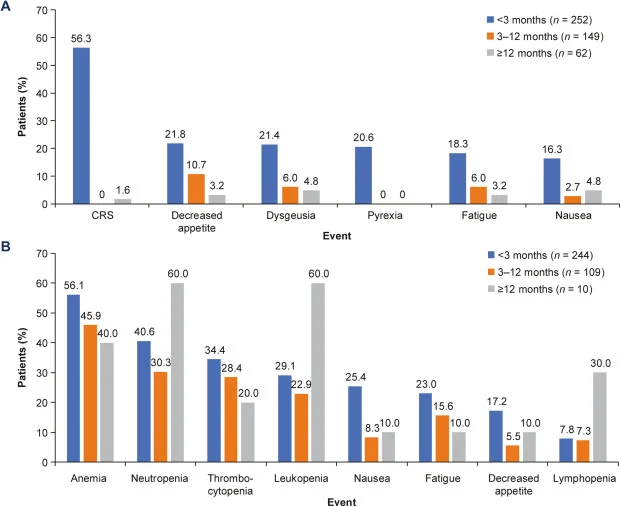
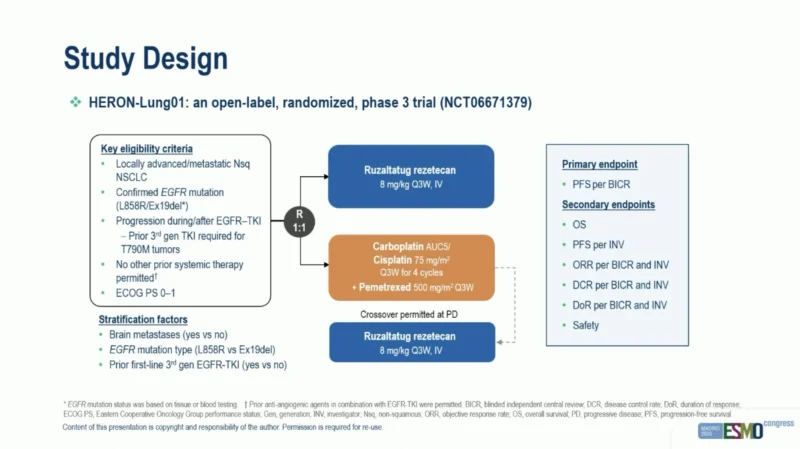
Dr. Chongrui Xu presents phase III HERON-Lung01 trial: ruzaltatug rezetecan (HER3 ADC) vs platinum chemo in EGFR NSCLC post TKI. ADC superior: PFS 8.3 vs 5.4m, HR 0.47 with OS trend (HR 0.70, ns) despite crossover. RR 60% vs 34% Low rates of discontinuation, ILD rate 2.4% and most toxicity hematologic.
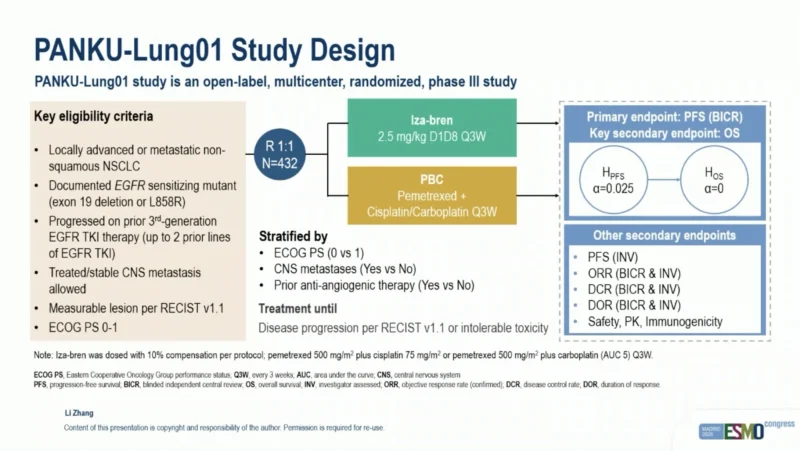
Dr. Li Zhang presents PANKU-Lung01: phase III izalontamab brengitecan (iza-bren, HER3:EGFR ADC) vs platinum based chemo in EGFR+ NSCLC after 3G TKI. Iza bren improved PFS: 11.1 vs 5.7m, HR 0.40! OS immature but 1y rates 83% vs 73%. High reduction/interruption rates but low discontinuation rates. Most common toxicities were hematologic in nature. Very exciting data here: ADCs here to stay.
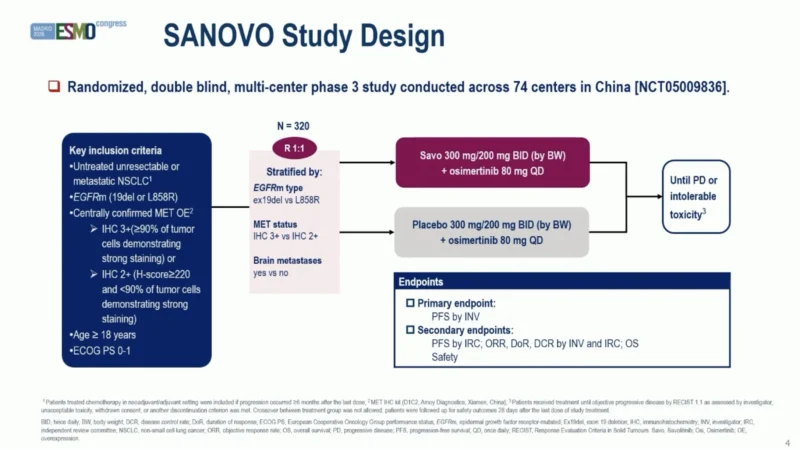
Dr. Yilong Wu presents SANOVO: 1L osimertinib + savolitinib/placebo in EGFR+ NSCLC with MET overexpression. Wow. PFS 24.8 vs 11.1m, HR 0.45 with OS 44.5 vs 34.9m, HR 0.48. RR 81% vs 68%. Toxicities below. Very impressive.”
You can also read:
25 Posts Not to Miss from ESMO Congress 2026: Day 3