






At ESMO 2026, Anders Ullén presented an ad hoc analysis of KEYNOTE-905/EV-303 (4733O), evaluating perioperative pembrolizumab alone or combined with enfortumab vedotin (EV) versus radical cystectomy with pelvic lymph-node dissection alone in patients with muscle-invasive bladder cancer who were ineligible for or declined cisplatin-based chemotherapy.
The analysis, included in the Proffered Paper session (4733O), assessed event-free survival (EFS), pathological complete response (pCR), and pathological downstaging in patients concurrently randomized to all three treatment arms.
Why Was This Analysis Conducted?
Primary results from KEYNOTE-905 demonstrated significant improvements in EFS, overall survival (OS), and pCR with perioperative EV plus pembrolizumab added to radical cystectomy and pelvic lymph-node dissection compared with surgery alone. The primary analysis included 344 patients randomized to EV plus pembrolizumab or control. The current ad hoc analysis evaluated outcomes with pembrolizumab alone and EV plus pembrolizumab compared with control among patients concurrently randomized to all three treatment arms.
KEYNOTE-905 Study Design and Methods
Eligible patients had centrally assessed T2–T4aN0M0 or T1–T4aN1M0 MIBC and were ineligible for or declined cisplatin. The study initially randomized patients to perioperative pembrolizumab or radical cystectomy alone. An EV plus pembrolizumab arm was added in August 2020. The ad hoc analysis included patients concurrently randomized to all three arms until randomization to pembrolizumab alone was discontinued in November 2022. Outcomes included EFS, pCR (pT0N0), and pathological downstaging (below pT2 and N0). No formal statistical testing was performed.

Key Findings from KEYNOTE-905
A total of 255 patients were included in the ad hoc analysis: 83 were randomized to pembrolizumab alone, 85 to EV plus pembrolizumab, and 87 to the control arm. At the June 6, 2025 data cutoff, median follow-up was 42.0 months (range 12.9–53.7).
Event-Free Survival
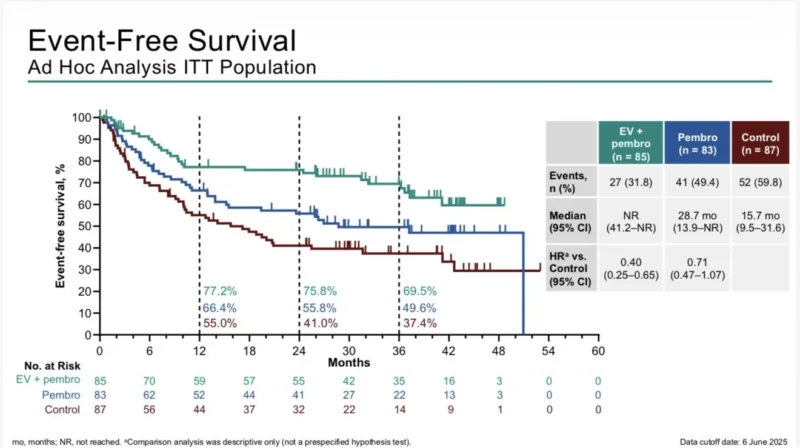
Median EFS was 28.7 months (95% CI 13.9–not reached) with pembrolizumab, not reached (95% CI 41.2–not reached) with EV plus pembrolizumab, and 15.7 months (95% CI 9.5–31.6) with control. At two years, estimated EFS rates were 55.8%, 75.8%, and 41.0%, respectively. Compared with control, the EFS hazard ratio was 0.71 (95% CI 0.47–1.07) for pembrolizumab alone and 0.40 (95% CI 0.25–0.65) for EV plus pembrolizumab.
Pathological Complete Response and Downstaging
The pCR rate was 25.3% (95% CI 16.4–36.0) with pembrolizumab, 58.8% (95% CI 47.6–69.4) with EV plus pembrolizumab, and 10.3% (95% CI 4.8–18.7) with control. Pathological downstaging rates were 33.7% (95% CI 23.7–44.9), 65.9% (95% CI 54.8–75.8), and 14.9% (95% CI 8.2–24.2), respectively. Both pembrolizumab-containing arms showed numerically higher pathological response and downstaging rates than control, with the highest rates observed in the EV plus pembrolizumab arm.
Safety Outcomes
Treatment-emergent adverse events occurred in 96% of patients receiving pembrolizumab, 100% receiving EV plus pembrolizumab, and 63% in the control arm. Grade 3 or higher events occurred in 70%, 69%, and 42% of patients, respectively.
Conclusions
The ad hoc KEYNOTE-905 analysis showed numerically favourable efficacy outcomes with perioperative EV plus pembrolizumab compared with radical cystectomy and pelvic lymph-node dissection alone, consistent with the primary study findings. Outcomes with pembrolizumab alone also suggested antitumour activity, although the ad hoc comparisons were descriptive and were not subject to formal hypothesis testing.
Source: ESMO Congress 2026 – Abstract 4733O, KEYNOTE-905/EV-303
Expert Highlights
Tom Powles, Head of Solid Tumor Research at Barts Cancer Institute, shared on X:
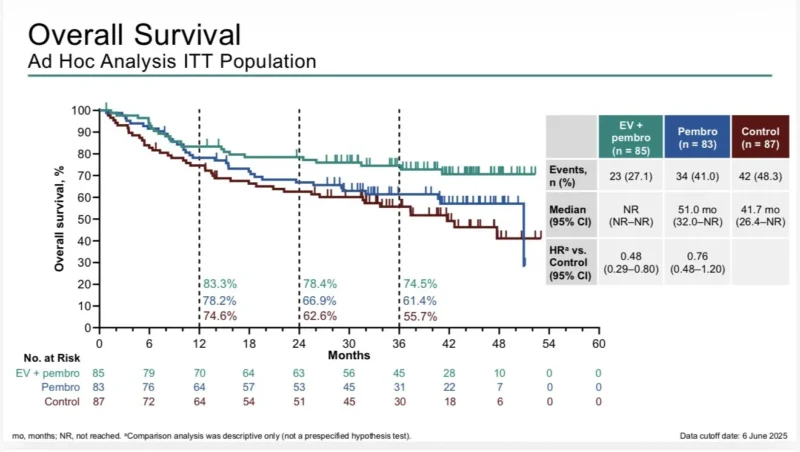
“The KN905 MIBC trial includes a 3rd, less celebrated arm of single agent pembro. Results show pembro delivers an important contribution to the EVP. The trial is small and EVP performs better, but pCR rates for pembro of 35% are in the same range as neoadjuvant cisplatin chemo while EFS/OS HRs of 0.71/O.76 vs surgery are impressive. Pembro had about half the toxicity of EVP, underlining the relevance of therapy duration. VOLGA (3 cycles of EVD), is a half way between Pembro alone and 9 cycles of EVP.”

Read more about KEYNOTE-866 at ESMO 2026 on OncoDaily.


