


Dabrafenib (Tafinlar): Understanding Its Mechanism, Dosing, Clinical Uses, and Role in BRAF V600–Mutated Cancers
Key takeaways
- Dabrafenib is a selective BRAF V600 inhibitor.
- The standard adult dose is 150 mg orally twice daily.
- It should be taken at least 1 hour before or 2 hours after food.
- Although FDA approved as monotherapy for BRAF V600E-mutant melanoma, it is now more commonly used with trametinib.
- Dabrafenib + trametinib is FDA approved for BRAF-mutant melanoma, metastatic NSCLC, anaplastic thyroid cancer, tumor-agnostic BRAF V600E solid tumors, and pediatric BRAF V600E low-grade glioma.
- COMBI-d and COMBI-v demonstrated durable benefit, with 5-year OS of 34% in pooled long-term analysis.
- ROAR demonstrated activity across several rare BRAF V600E-mutant cancers.
- In pediatric BRAF V600E LGG, dabrafenib/trametinib achieved an ORR of 46.6% vs 10.8% with carboplatin/vincristine and median PFS of 20.1 vs 7.4 months.
- Major safety priorities include pyrexia, secondary malignancies, hemorrhage, cardiac effects, ocular toxicity, severe skin reactions, and hyperglycemia.
- In 2026, dabrafenib is best understood primarily as part of dual BRAF/MEK blockade, rather than as isolated BRAF monotherapy.
Dabrafenib (Tafinlar) is an oral, selective inhibitor of mutant BRAF kinase, particularly BRAF V600E and BRAF V600K. It was developed to suppress constitutive MAPK-pathway activation in tumors driven by activating BRAF mutations and has become a central component of BRAF/MEK combination therapy, most commonly with trametinib.
Dabrafenib is FDA approved as single-agent therapy for unresectable or metastatic BRAF V600E-mutant melanoma and, more importantly in current practice, in combination with trametinib for several BRAF V600-driven malignancies, including melanoma, metastatic NSCLC, anaplastic thyroid cancer, tumor-agnostic BRAF V600E-positive solid tumors, and pediatric low-grade glioma. The current US label also includes a pediatric oral-suspension formulation and indications beginning at 1 year of age for selected BRAF V600E-positive tumors.
Key Facts
- Generic name: Dabrafenib
- Brand name: Tafinlar
- Drug class: BRAF kinase inhibitor
- Route: Oral
- Initial US approval: 2013
- Primary target: Mutant BRAF
- Most relevant mutations: BRAF V600E and V600K
- Adult dose: 150 mg orally twice daily
- Administration: At least 1 hour before or at least 2 hours after a meal
- Capsule strengths: 50 mg and 75 mg
- Pediatric formulation: 10 mg tablets for oral suspension
- Common combination: Dabrafenib + trametinib
- Major safety issues: Pyrexia, new primary malignancies, hemorrhage, cardiomyopathy when combined with trametinib, ocular toxicity, severe skin reactions, hyperglycemia, and G6PD-related hemolysis risk
- Major metabolism: CYP2C8 and CYP3A4
- Current US status: FDA approved.
What Is Dabrafenib?
Dabrafenib is a small-molecule inhibitor of mutant BRAF.
The BRAF protein is part of the:
RAS–RAF–MEK–ERK signaling pathway
which regulates:
- Cell proliferation
- Cell survival
- Differentiation
- Migration
- Growth
In tumors harboring activating BRAF V600 mutations, BRAF becomes constitutively active and continuously stimulates downstream MEK and ERK signaling.
This can drive malignant growth even in the absence of upstream receptor signaling.
Dabrafenib suppresses this abnormal kinase activity.
What Is the Mechanism of Action of Dabrafenib?
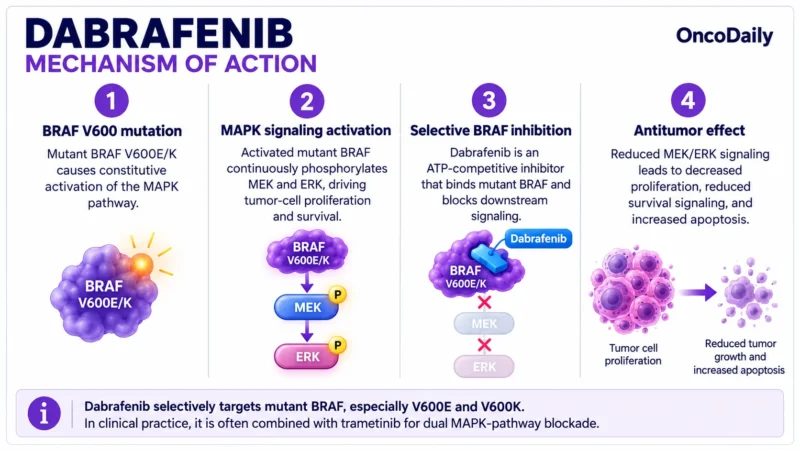
1. BRAF V600 Mutation Constitutively Activates BRAF
The most clinically relevant mutations include:
- BRAF V600E
- BRAF V600K
These alterations promote persistent kinase activity.
2. MAPK Signaling Becomes Continuously Active
Mutant BRAF activates:
MEK1/2
which activates:
ERK1/2.
This leads to:
- Increased proliferation
- Increased survival
- Tumor growth
- Reduced apoptosis
3. Dabrafenib Binds Mutant BRAF
Dabrafenib is an:
ATP-competitive BRAF kinase inhibitor.
It binds the ATP-binding site of mutant BRAF and suppresses kinase activity.
4. MEK and ERK Activation Falls
BRAF inhibition reduces downstream:
- MEK phosphorylation
ERK phosphorylation
and therefore suppresses MAPK-pathway signaling.
5. Tumor Growth Is Reduced
The result is:
- Reduced proliferation
- Reduced survival signaling
- Increased apoptosis
- Tumor regression in BRAF-dependent cancers
The mechanism can be summarized as:
Dabrafenib → mutant BRAF inhibition → reduced MEK/ERK signaling → decreased tumor-cell proliferation and survival.
Why Is Dabrafenib Usually Combined With Trametinib?
BRAF inhibition alone can produce rapid responses, but resistance frequently develops through reactivation of the:
MAPK pathway.
Trametinib inhibits:
MEK1/2
downstream of BRAF.
Therefore:
Dabrafenib + trametinib
provides dual blockade of the pathway.
This combination:
- Improves response durability
- Prolongs PFS
- Improves overall survival
- Reduces some paradoxical MAPK-mediated secondary skin tumors compared with BRAF monotherapy
This is why combination therapy is preferred in most modern BRAF V600-mutated settings.
What Is the Dose of Dabrafenib?
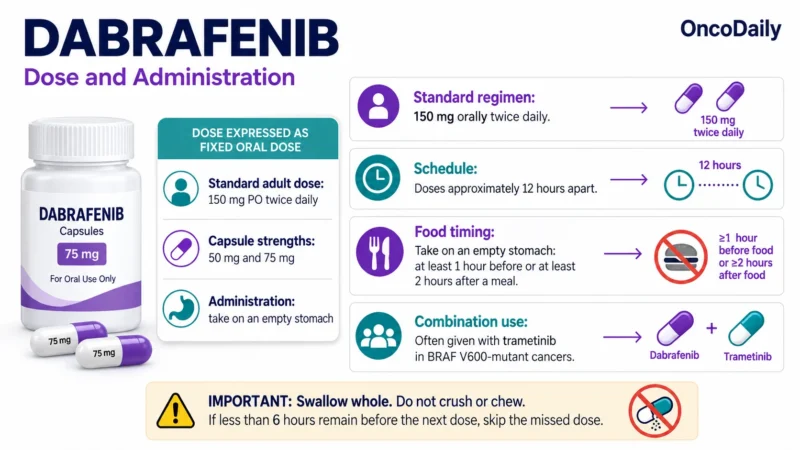
Adults
The recommended adult dose is:
150 mg orally twice daily.
This applies whether dabrafenib is being used:
- Alone
- With trametinib
unless a dose modification is required.
Doses should be taken approximately:
12 hours apart.
Dabrafenib should be taken:
At least 1 hour before or at least 2 hours after a meal. Access
What If a Dose Is Missed?
If a dose is missed:
Take it when remembered only if there are:
More than 6 hours before the next scheduled dose.
If fewer than 6 hours remain:
Skip the missed dose.
Do not take two doses at the same time.
If vomiting occurs after dabrafenib:
Do not repeat the dose.
Take the next scheduled dose at the usual time.
How Are Dabrafenib Dose Reductions Made?
For adults, the standard dose is:
150 mg twice daily.
Typical reductions are:
- 100 mg twice daily
- 75 mg twice daily
- 50 mg twice daily
If the patient cannot tolerate:
50 mg twice daily
treatment should generally be discontinued.
Dose interruption or reduction may be required for:
- Pyrexia
- Severe skin toxicity
- Hyperglycemia
- Uveitis
- Hemorrhage
- Other Grade ≥3 toxicities
Certain toxicities related primarily to trametinib may require modifying trametinib rather than dabrafenib.
How Is Dabrafenib Administered?
Dabrafenib is available as:
- 50 mg capsules
- 75 mg capsules
- 10 mg tablets for oral suspension
Capsules should be:
- Swallowed whole
- Not opened
- Not crushed
- Not broken
It should be administered:
At least 1 hour before or at least 2 hours after food.
Unlike vemurafenib, dabrafenib should not routinely be taken with meals because food reduces absorption.
Pediatric Dosing
For pediatric patients, dosing is:
Weight based.
The current label includes patients:
1 year of age and older
for selected indications.
Examples from the current dosing table include:
- 26–29 kg: 70 mg twice daily
- 30–33 kg: 80 mg twice daily
- 34–37 kg: 90 mg twice daily
- 38–41 kg: 100 mg twice daily
- 42–45 kg: 110 mg twice daily
- 46–50 kg: 130 mg twice daily
- ≥51 kg: 150 mg twice daily.
Younger and lower-weight children use the oral-suspension formulation according to the label’s weight-based schedule.
What Are the Important Drug Interactions With Dabrafenib?
Dabrafenib is metabolized mainly by:
CYP2C8
and:
CYP3A4.
Strong CYP2C8 or CYP3A4 Inhibitors
These may increase dabrafenib exposure and toxicity.
Examples include:
- Gemfibrozil
- Ketoconazole
- Clarithromycin
- Itraconazole
Clinical alternatives should be considered when possible.
CYP Induction by Dabrafenib
Dabrafenib can induce several enzymes, including:
- CYP3A4
- CYP2C9
- CYP2C8
- CYP2B6
and can therefore reduce exposure to other medications.
This is clinically important for drugs with narrow therapeutic windows.
Hormonal Contraceptives
Dabrafenib may reduce the effectiveness of hormonal contraceptives.
Patients should use:
Effective non-hormonal contraception.
Does Dabrafenib Require Renal or Hepatic Dose Adjustment?
Renal Impairment
No clinically meaningful pharmacokinetic change is expected in:
Mild-to-moderate renal impairment.
Data are limited in severe renal impairment.
Hepatic Impairment
No routine adjustment is generally required for:
Mild hepatic impairment.
Data are limited in moderate or severe hepatic impairment, so these patients require careful clinical monitoring.
What Is the Pharmacokinetic Profile of Dabrafenib?
Absorption
Dabrafenib is rapidly absorbed following oral administration.
Peak concentrations generally occur within:
Approximately 2 hours.
Food Effect
Food reduces dabrafenib exposure.
Therefore it should be taken:
At least 1 hour before or 2 hours after a meal.
Protein Binding
Dabrafenib is highly protein bound.
Metabolism
Primary metabolism occurs through:
- CYP2C8
- CYP3A4
Active metabolites include:
- Hydroxy-dabrafenib
- Desmethyl-dabrafenib
Half-Life
The terminal half-life of dabrafenib is approximately:
8 hours
although some active metabolites persist longer.
Elimination
Elimination occurs primarily through:
Fecal excretion
with a smaller urinary component.
What Are the Clinical Uses of Dabrafenib?
The current FDA label includes several important indications.
1. BRAF V600E-Mutant Unresectable or Metastatic Melanoma — Single Agent
Dabrafenib is FDA approved as a single agent for:
Unresectable or metastatic melanoma with a BRAF V600E mutation.
However, combination therapy is preferred in contemporary practice.
2. BRAF V600E or V600K Unresectable or Metastatic Melanoma
In combination with trametinib, dabrafenib is approved for:
Unresectable or metastatic melanoma with BRAF V600E or V600K mutation.
3. Adjuvant Melanoma
Dabrafenib plus trametinib is approved for:
Adjuvant treatment after complete resection of melanoma with BRAF V600E or V600K mutation and lymph-node involvement.
4. BRAF V600E-Mutant Metastatic NSCLC
Dabrafenib plus trametinib is approved for:
Metastatic NSCLC with BRAF V600E mutation.
5. BRAF V600E-Mutant Anaplastic Thyroid Cancer
The combination is approved for:
Locally advanced or metastatic BRAF V600E-positive anaplastic thyroid cancer with no satisfactory locoregional treatment options.
6. BRAF V600E-Mutant Unresectable or Metastatic Solid Tumors
Dabrafenib plus trametinib is approved for:
Adults and pediatric patients aged 1 year and older with unresectable or metastatic BRAF V600E-mutant solid tumors that have progressed after prior treatment and have no satisfactory alternative therapy.
This is a:
Tumor-agnostic accelerated approval.
Important limitation:
It is not indicated for colorectal cancer because of known intrinsic resistance to BRAF inhibition.
7. Pediatric BRAF V600E-Mutant Low-Grade Glioma
Dabrafenib plus trametinib is approved for:
Pediatric patients aged 1 year and older with BRAF V600E-mutant low-grade glioma requiring systemic therapy.
What Did Dabrafenib Clinical Trials Show?
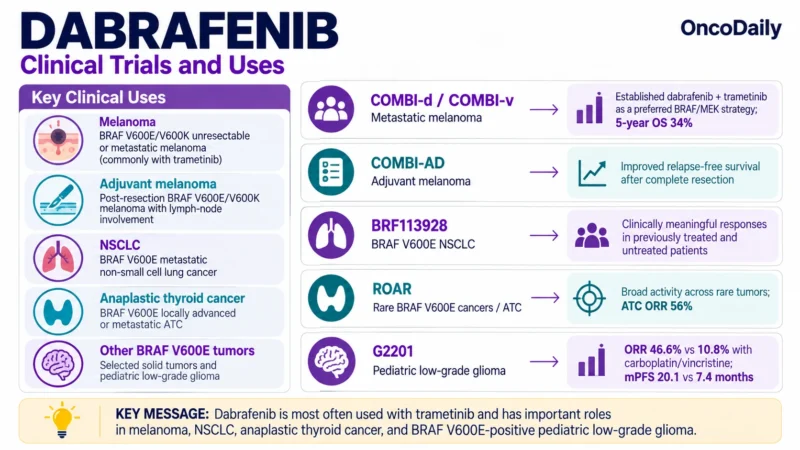
COMBI-d — Dabrafenib + Trametinib Versus Dabrafenib Alone
COMBI-d evaluated previously untreated patients with:
BRAF V600E/K-mutated unresectable or metastatic melanoma.
Patients received:
- Dabrafenib 150 mg twice daily + trametinib 2 mg once daily
- Dabrafenib alone
The combination significantly improved disease control compared with dabrafenib monotherapy.
Long-term pooled analysis of COMBI-d and COMBI-v showed durable benefit, with:
- 5-year PFS: 19%
- 5-year OS: 34%
among patients treated with dabrafenib plus trametinib.
Patients achieving a complete response had particularly favorable outcomes, with:
5-year OS approximately 71%.
COMBI-v — Dabrafenib + Trametinib Versus Vemurafenib
COMBI-v directly compared:
Dabrafenib + trametinib
with:
Vemurafenib monotherapy
in previously untreated BRAF V600-mutant metastatic melanoma.
The combination significantly improved:
- Overall survival
- Progression-free survival
- Response rate
and established combined BRAF/MEK inhibition as a preferred targeted approach.
The long-term pooled COMBI-d/COMBI-v analysis confirmed that approximately one-third of patients remained alive at 5 years.
COMBI-AD — Adjuvant Melanoma
COMBI-AD evaluated dabrafenib plus trametinib for one year after complete resection of:
Stage III BRAF V600E/K-mutant melanoma.
The combination significantly reduced the risk of:
- Recurrence
- Distant metastasis
compared with placebo.
These results established dabrafenib/trametinib as an important adjuvant targeted-treatment option in resected BRAF-mutant melanoma.
BRF113928 — BRAF V600E-Mutant NSCLC
The phase II BRF113928 study evaluated dabrafenib plus trametinib in metastatic BRAF V600E-positive NSCLC.
The current FDA label includes:
- 36 previously untreated patients
- 57 previously treated patients
treated with dabrafenib 150 mg twice daily plus trametinib 2 mg once daily.
The study demonstrated clinically meaningful objective responses in both cohorts and supported FDA approval for BRAF V600E-positive metastatic NSCLC.
ROAR — Anaplastic Thyroid Cancer
The phase II ROAR basket trial evaluated dabrafenib plus trametinib in BRAF V600E-mutant rare cancers.
In the anaplastic thyroid cancer cohort:
n = 36
Objective Response Rate
ORR was:
56%.
Median Progression-Free Survival
6.7 months.
Median Overall Survival
14.5 months.
24-Month Overall Survival
31.5%.
ROAR — BRAF V600E Rare Tumors
Final ROAR results demonstrated activity across several BRAF V600E-mutant rare cancers.
Reported investigator-assessed ORRs included:
- Anaplastic thyroid cancer: 56%
- Biliary tract cancer: 53%
- Low-grade glioma: 54%
- High-grade glioma: 33%
- Hairy cell leukemia: 89%
- Multiple myeloma: 50%.
This broad activity contributed to the tumor-agnostic development of dabrafenib plus trametinib.
BRAF V600E-Mutant Biliary Tract Cancer
Within ROAR:
43 patients
with previously treated BRAF V600E-mutant biliary tract cancer were evaluated.
The initial analysis reported:
- Investigator-assessed ORR: 51%
- Independent-review ORR: 47%.
The final ROAR analysis reported an ORR of approximately:
53%.
Adult BRAF V600E-Mutant Glioma
In ROAR:
High-Grade Glioma
45 patients
ORR:
33%.
Low-Grade Glioma
13 patients
ORR:
69% in the published interim analysis.
These data demonstrated clinically meaningful CNS activity of dual BRAF/MEK blockade.
Pediatric Low-Grade Glioma — G2201
The randomized CDRB436G2201 trial evaluated first-line systemic treatment in children with BRAF V600E-mutant low-grade glioma.
A total of:
110 patients
were randomized:
- Dabrafenib + trametinib: 73
- Carboplatin + vincristine: 37
Objective Response Rate
- Dabrafenib + trametinib: 46.6%
- Carboplatin + vincristine: 10.8%
P < 0.001.
Median Progression-Free Survival
- Dabrafenib + trametinib: 20.1 months
- Carboplatin + vincristine: 7.4 months
Hazard ratio:
0.31.
This became the first FDA-approved systemic first-line therapy specifically for pediatric BRAF V600E-positive low-grade glioma.
Is Dabrafenib FDA Approved?
Yes.
Dabrafenib received its initial FDA approval in:
2013.
Its indications have expanded considerably and now include single-agent and combination uses across multiple BRAF-driven cancers.
What Is the Current Clinical Role of Dabrafenib?
Melanoma
In advanced BRAF V600E/K-mutated melanoma, dabrafenib is generally used:
With trametinib rather than alone.
The combination offers:
- More durable responses
- Longer PFS
- Better OS
- Reduced paradoxical skin-tumor risk compared with BRAF monotherapy
However, immune checkpoint therapy is also central in modern melanoma treatment, so sequencing depends on:
- Symptoms
- Disease burden
- CNS disease
- LDH
- Need for rapid tumor shrinkage
- Prior therapy
NSCLC
For BRAF V600E-positive metastatic NSCLC, dabrafenib plus trametinib remains a well-established targeted regimen.
Anaplastic Thyroid Cancer
In BRAF V600E-positive ATC, dabrafenib plus trametinib remains especially important because of the aggressive natural history and high response rate relative to historical systemic therapy.
Tumor-Agnostic BRAF V600E Disease
The combination has a broader FDA indication for previously treated BRAF V600E-positive solid tumors without satisfactory alternatives, although:
Colorectal cancer is specifically excluded because BRAF inhibition alone is biologically insufficient in that disease.
Pediatric Low-Grade Glioma
Dabrafenib plus trametinib is now a major precision-treatment option in BRAF V600E-positive pediatric LGG, including first-line systemic therapy.
Read more: OncoDaily’s summary of the ASCO Living Guideline 2026.3.0, including current recommendations for BRAF V600E-mutated NSCLC and the role of dabrafenib plus trametinib.
Watch more: Explore OncoDaily’s discussion on targeted therapies and the evolving treatment landscape for oncogene-driven cancers.
What Are the Major Side Effects of Dabrafenib?
Common adverse effects vary by indication and whether dabrafenib is used alone or with trametinib.
Frequently reported effects include:
- Pyrexia
- Fatigue
- Rash
- Chills
- Nausea
- Vomiting
- Diarrhea
- Headache
- Arthralgia
- Myalgia
- Dry skin.
Pyrexia
Fever is one of the most characteristic toxicities of dabrafenib plus trametinib.
Pyrexia may be associated with:
- Chills
- Rigors
- Dehydration
- Hypotension
- Renal dysfunction
For clinically significant fever:
- Hold therapy
- Assess for infection
- Ensure hydration
- Resume according to severity and recovery
Recurrent pyrexia may require:
- Dose interruption
- Dose reduction
- Antipyretic treatment
- Short-course corticosteroids in selected recurrent cases
New Primary Malignancies
Dabrafenib can promote new malignancies through paradoxical MAPK activation in wild-type BRAF cells.
These may include:
- Cutaneous squamous-cell carcinoma
- Keratoacanthoma
- New primary melanoma
- Noncutaneous malignancies
Patients require:
- Dermatologic examination before treatment
- Periodic skin examination during therapy
- Continued surveillance after treatment.
Tumor Promotion in BRAF Wild-Type Tumors
BRAF inhibitors can paradoxically stimulate MAPK signaling in certain cells with:
Wild-type BRAF.
Therefore dabrafenib should not be used for tumors without a qualifying BRAF mutation.
Hemorrhage
Serious hemorrhagic events can occur, particularly with:
Dabrafenib + trametinib.
Patients should be monitored for:
- Gastrointestinal bleeding
- Intracranial hemorrhage
- Other clinically significant bleeding
Severe events may require permanent discontinuation.
Cardiomyopathy
When combined with trametinib, treatment can reduce:
Left ventricular ejection fraction.
Monitoring should include:
- Baseline LVEF
- Repeat cardiac assessment during treatment when indicated
Clinically significant cardiomyopathy may require:
- Treatment interruption
- Dose modification
- Permanent discontinuation
Ocular Toxicity
Possible ocular toxicities include:
- Uveitis
- Iritis
- Retinal pigment epithelial detachment when used with trametinib
- Retinal vein occlusion related to MEK inhibition
Patients with:
- Eye pain
- Photophobia
- Blurred vision
- Visual changes
require prompt ophthalmologic evaluation.
Serious Skin Reactions
Severe skin reactions can include:
- Stevens-Johnson syndrome
- Toxic epidermal necrolysis
- DRESS
Severe or life-threatening reactions require:
Permanent discontinuation.
Hyperglycemia
Dabrafenib may worsen:
Blood glucose control.
This is particularly relevant in patients with:
- Diabetes mellitus
- Prediabetes
Glucose should be monitored when clinically appropriate.
G6PD Deficiency and Hemolytic Anemia
Dabrafenib contains a sulfonamide moiety and may increase the risk of:
Hemolytic anemia in patients with G6PD deficiency.
These patients should be monitored for:
- Falling hemoglobin
- Jaundice
- Hemolysis symptoms
Embryo-Fetal Toxicity
Dabrafenib can cause fetal harm.
Patients of reproductive potential should use effective contraception.
Because dabrafenib may reduce hormonal contraceptive effectiveness:
Non-hormonal contraception is preferred.
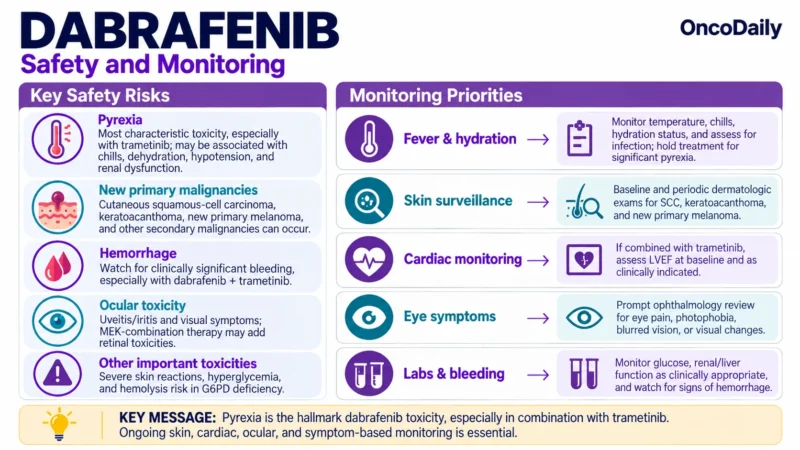
What Monitoring Is Required?
Monitoring during dabrafenib therapy should include:
- Confirmed BRAF mutation before treatment
- Dermatologic examination
- Temperature and symptoms of pyrexia
- Hydration status
- CBC when clinically indicated
- Glucose
- Liver function
- Renal function
- Visual symptoms
- Cardiac function when used with trametinib
- Signs of bleeding
- Signs of secondary malignancies
- Concomitant CYP2C8/CYP3A4 medications
- Pregnancy counseling
When used with trametinib, monitoring also includes:
- LVEF
- Pulmonary symptoms
- Ocular symptoms
- Skin toxicity
FAQ
What Is Dabrafenib Used For?
What Is the Standard Adult Dose?
Should Dabrafenib Be Taken With Food?
Take it:
At least 1 hour before or at least 2 hours after a meal.
Why Is Dabrafenib Combined With Trametinib?
What Did COMBI-d and COMBI-v Show?
- 5-year PFS: 19%
- 5-year OS: 34%.
Is Dabrafenib Used in NSCLC?
Dabrafenib plus trametinib is FDA approved for:
BRAF V600E-positive metastatic NSCLC.
Is Dabrafenib Used in Thyroid Cancer?
The combination is approved for:
BRAF V600E-positive locally advanced or metastatic anaplastic thyroid cancer.
Is Dabrafenib Tumor-Agnostic?
Is Dabrafenib Used in Children?
Current FDA indications include patients 1 year and older for selected BRAF V600E-positive solid tumors and low-grade glioma.