Yago Garitaonaindía, Translational Research Fellow at CCIT-DK – National Center for Cancer Immune Therapy of Denmark, shared a post on X by Stephen V Liu, Chief of the Division of Hematology and Oncology, and Associate Professor at Georgetown Lombardi Comprehensive Cancer Center, adding:
“Compelling results from MDT-BRIDGE WCLC26
Two personal takeaways/ideas:
- Stop calling full resectability upfront: assess it after neoadjuvant chemo-IO, when the tumor has already shown you what it does.
- The value is in the sequence, not just the drug. Prime with IO, let the immune response settle, then irradiate.
Personal opinion: it will hold in upfront unresectable disease too (APOLO).”
Quoting Stephen V Liu’s post:
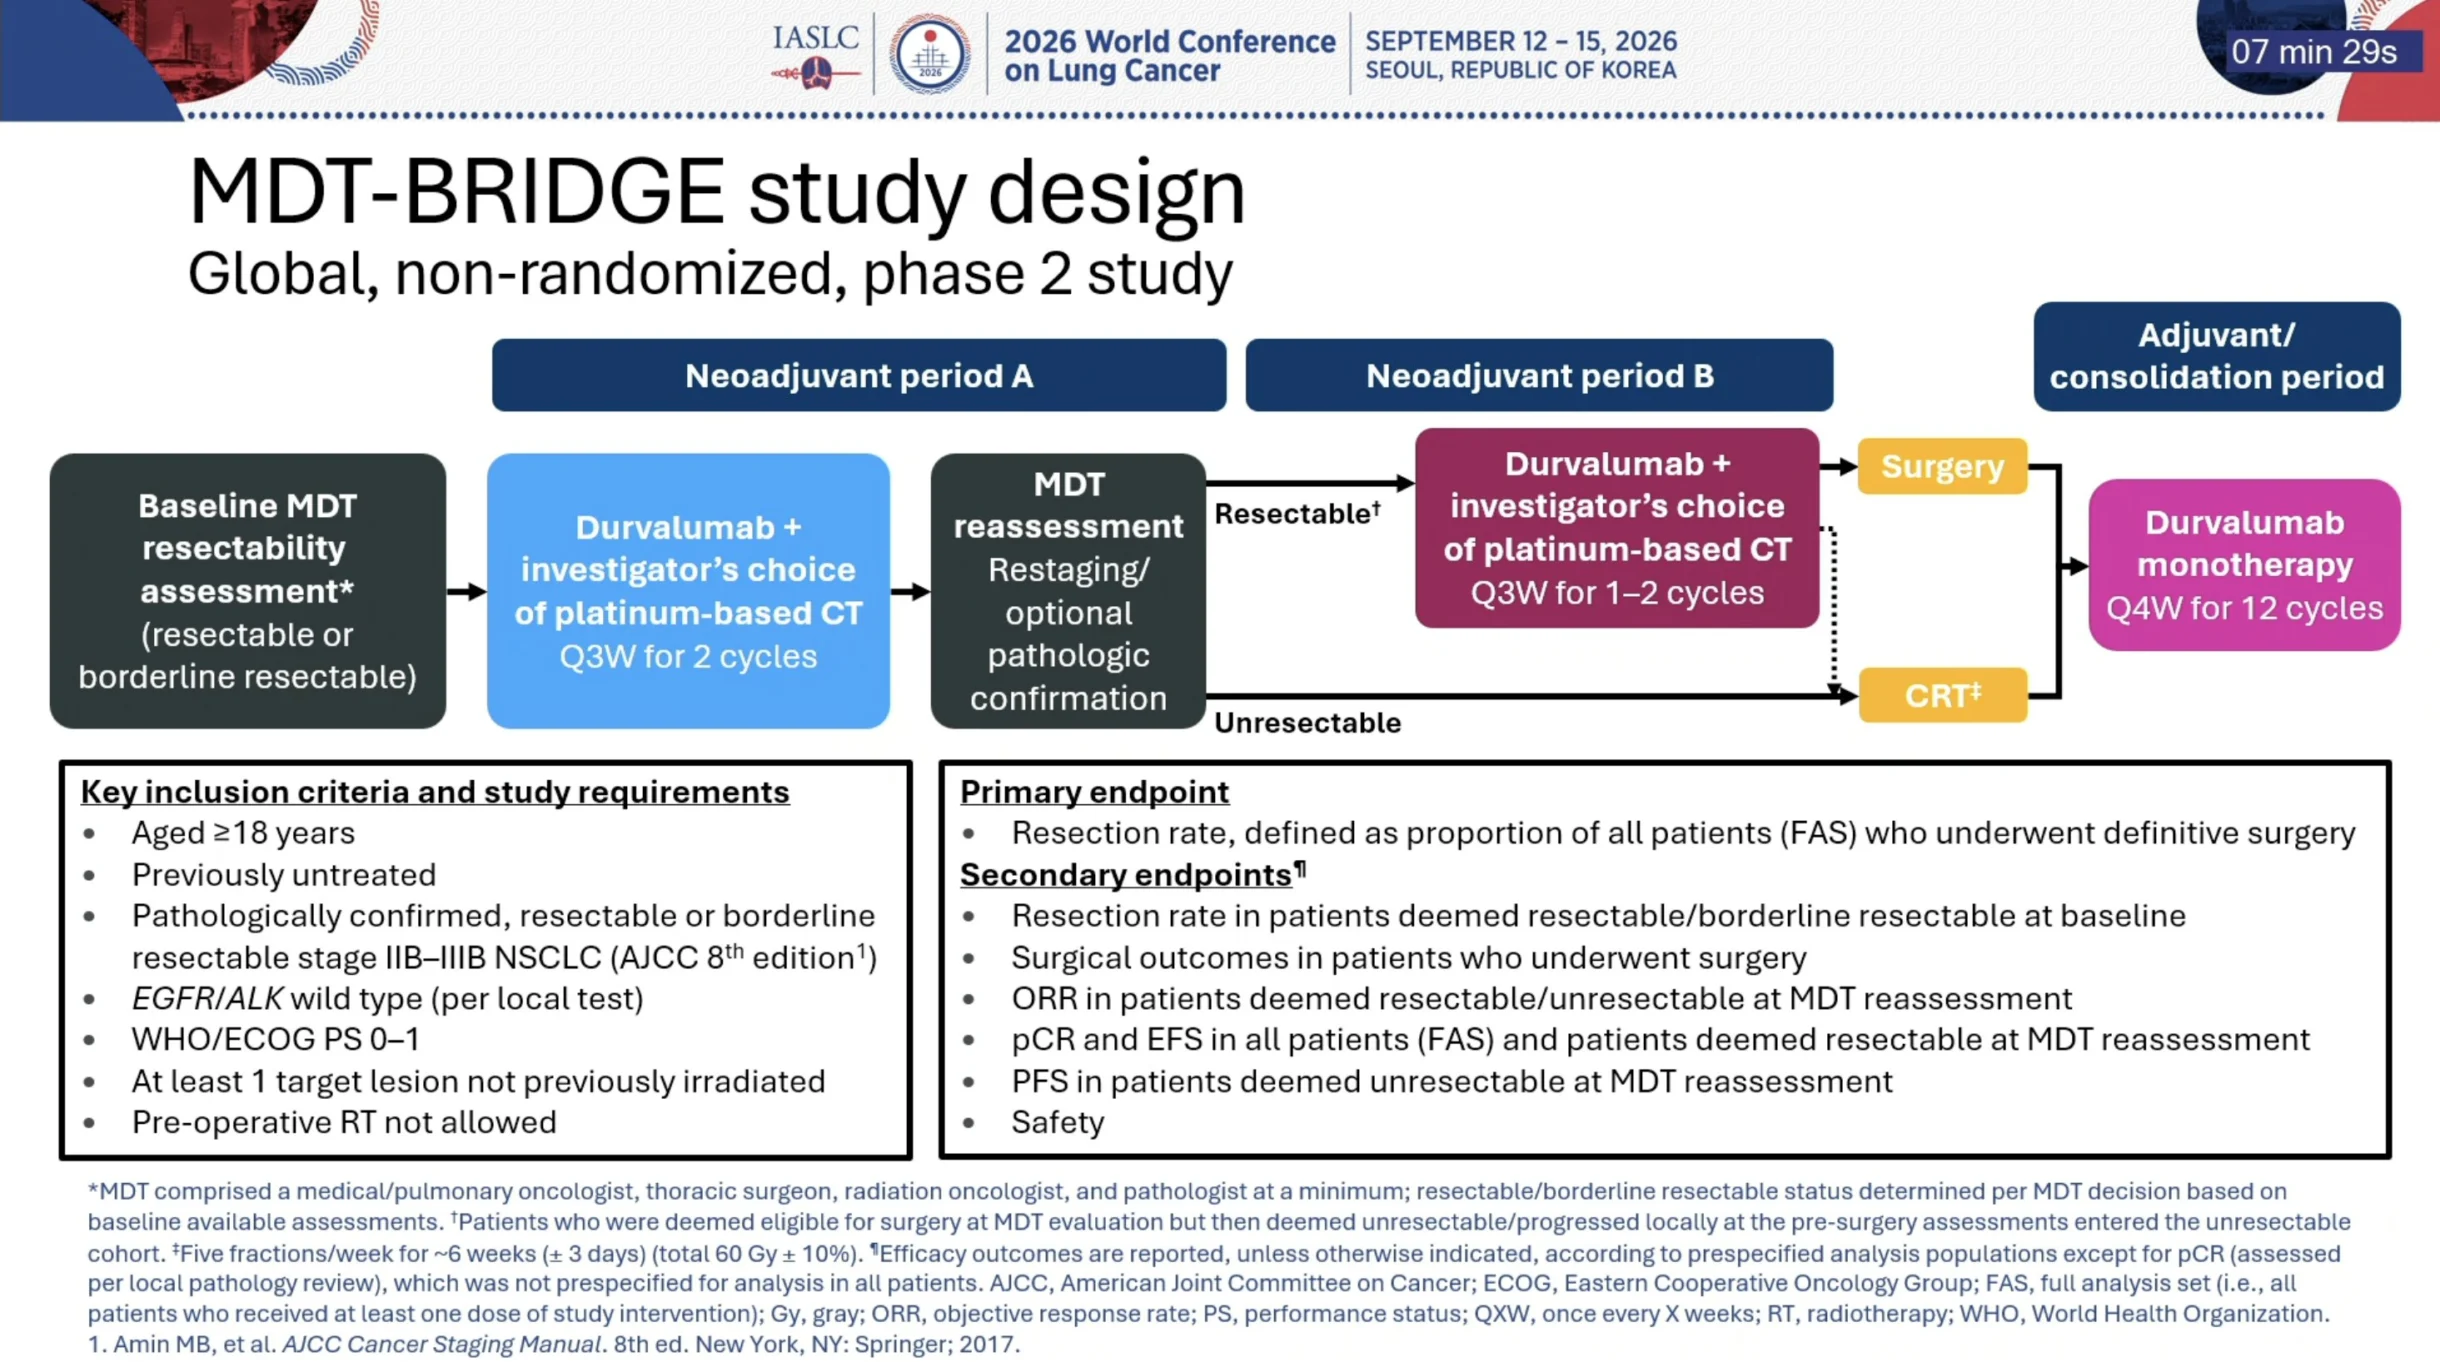
“Dr. Martin Reck presents MDT-Bridge at WCLC26: pts with resectable or borderline resectable NSCLC received 1-2 cycles of durvalumab + chemotherapy then surgery if resectable or CRT if not, followed by adjuvant/consolidation durvalumab.
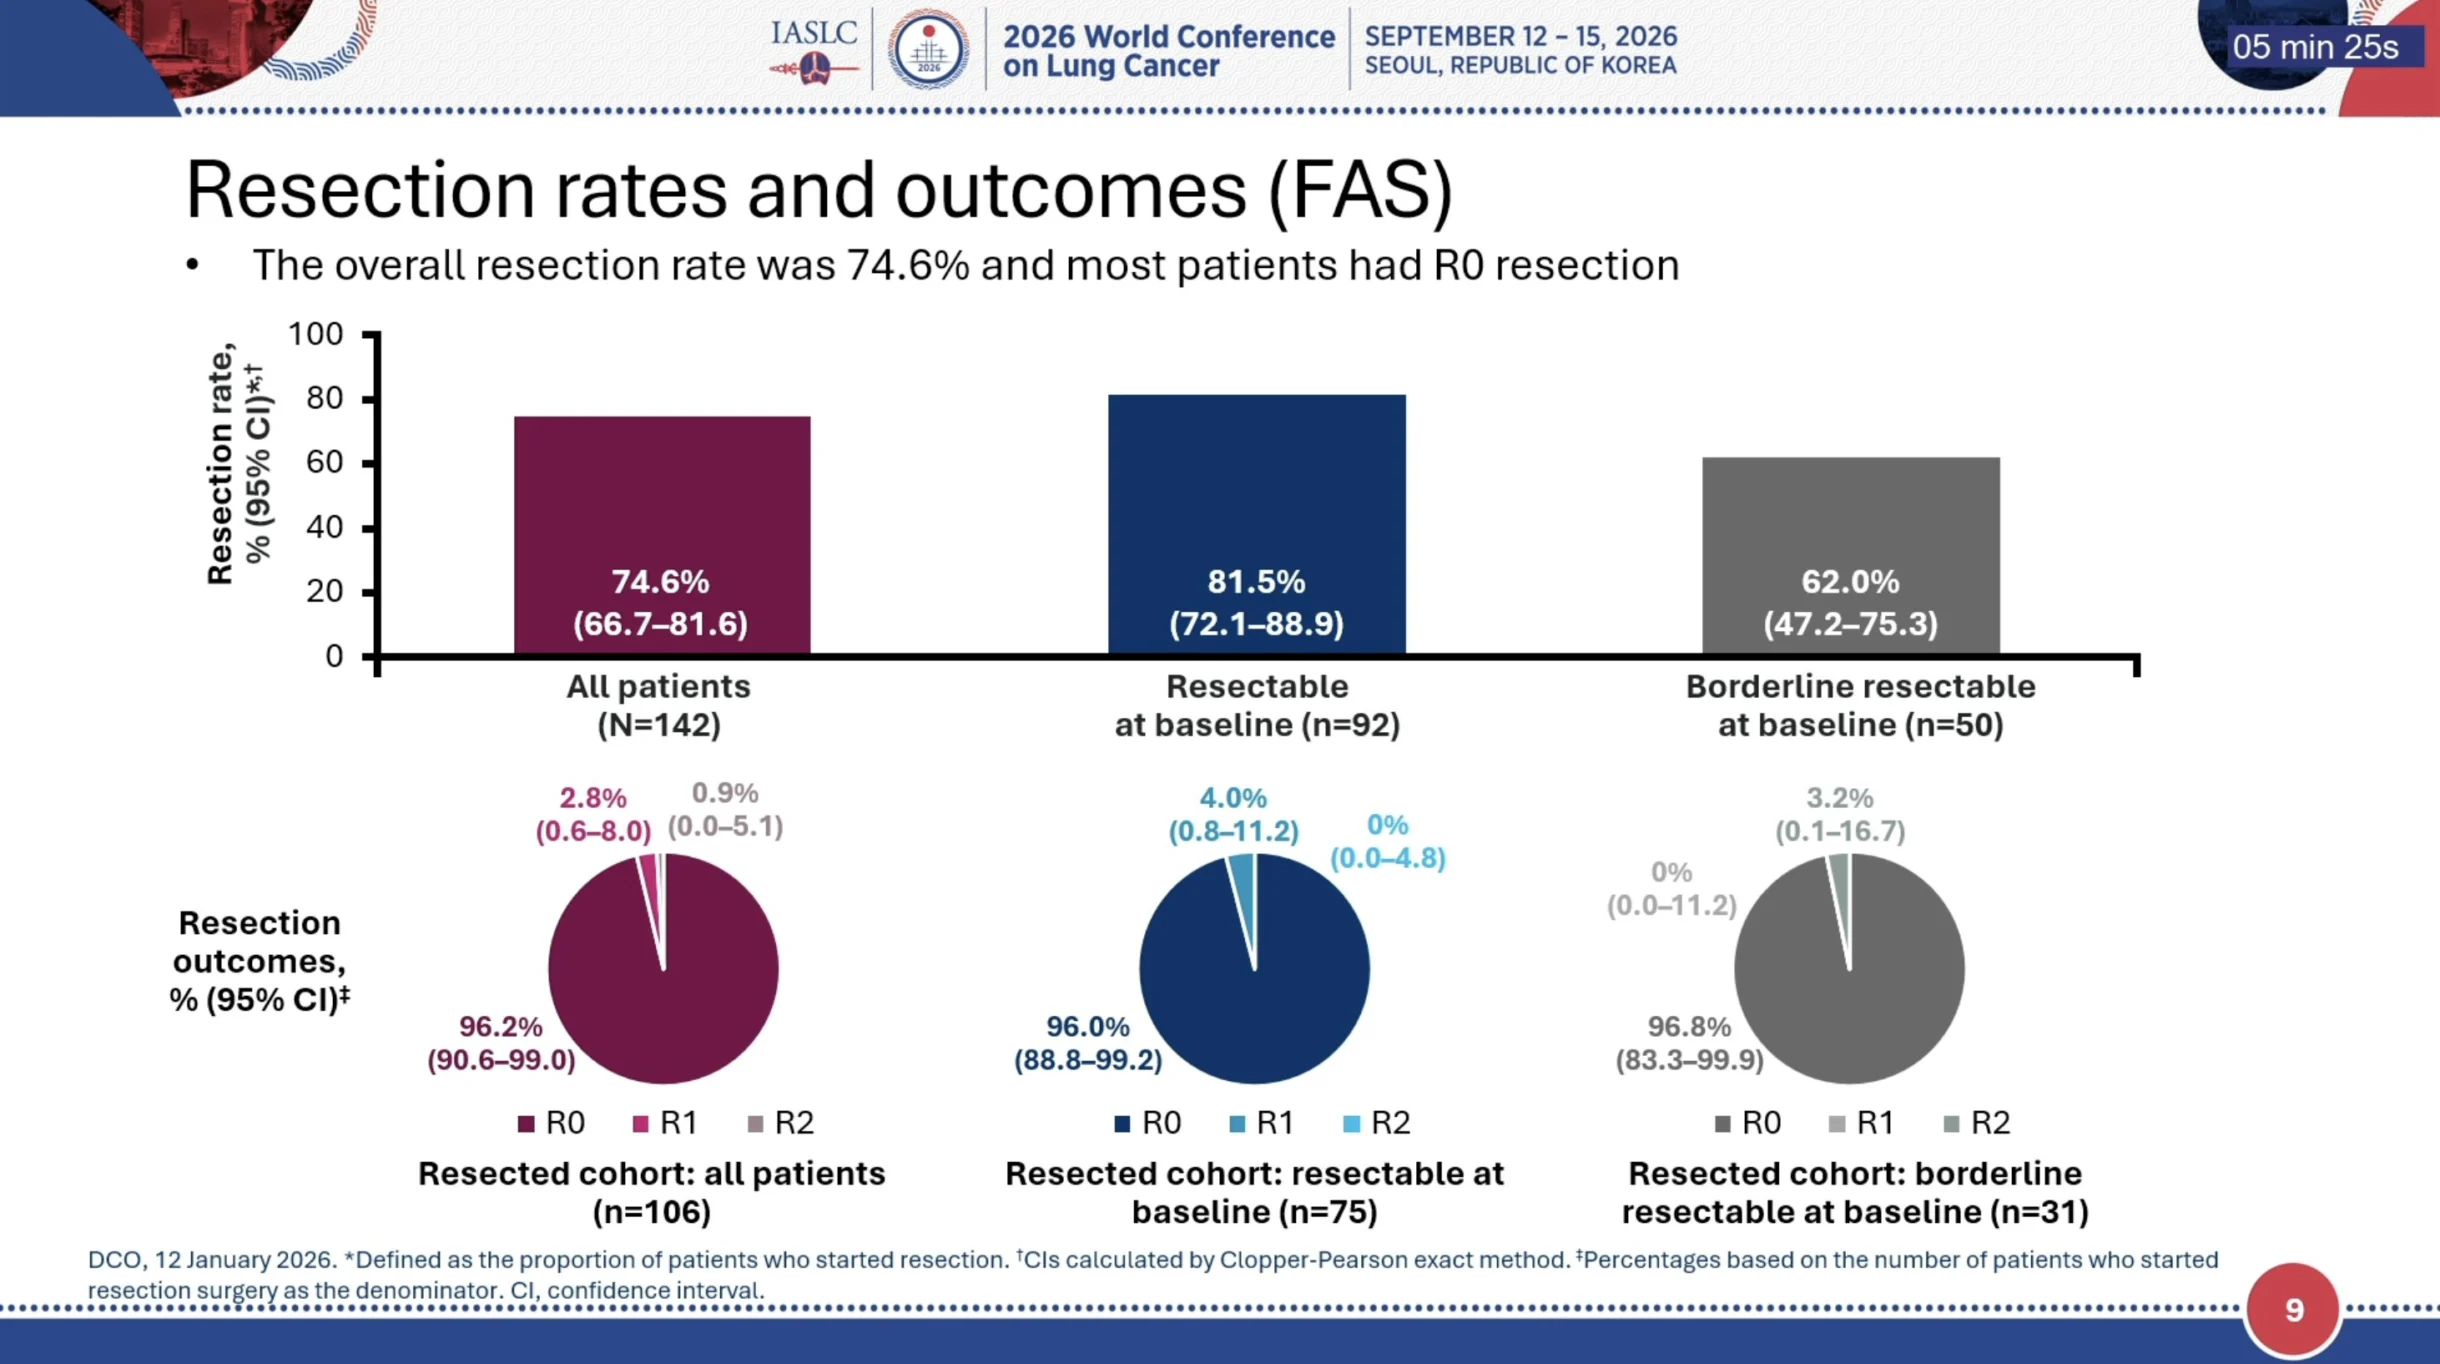
Of those with borderline resectable NSCLC, 62% underwent resection (97% R0).
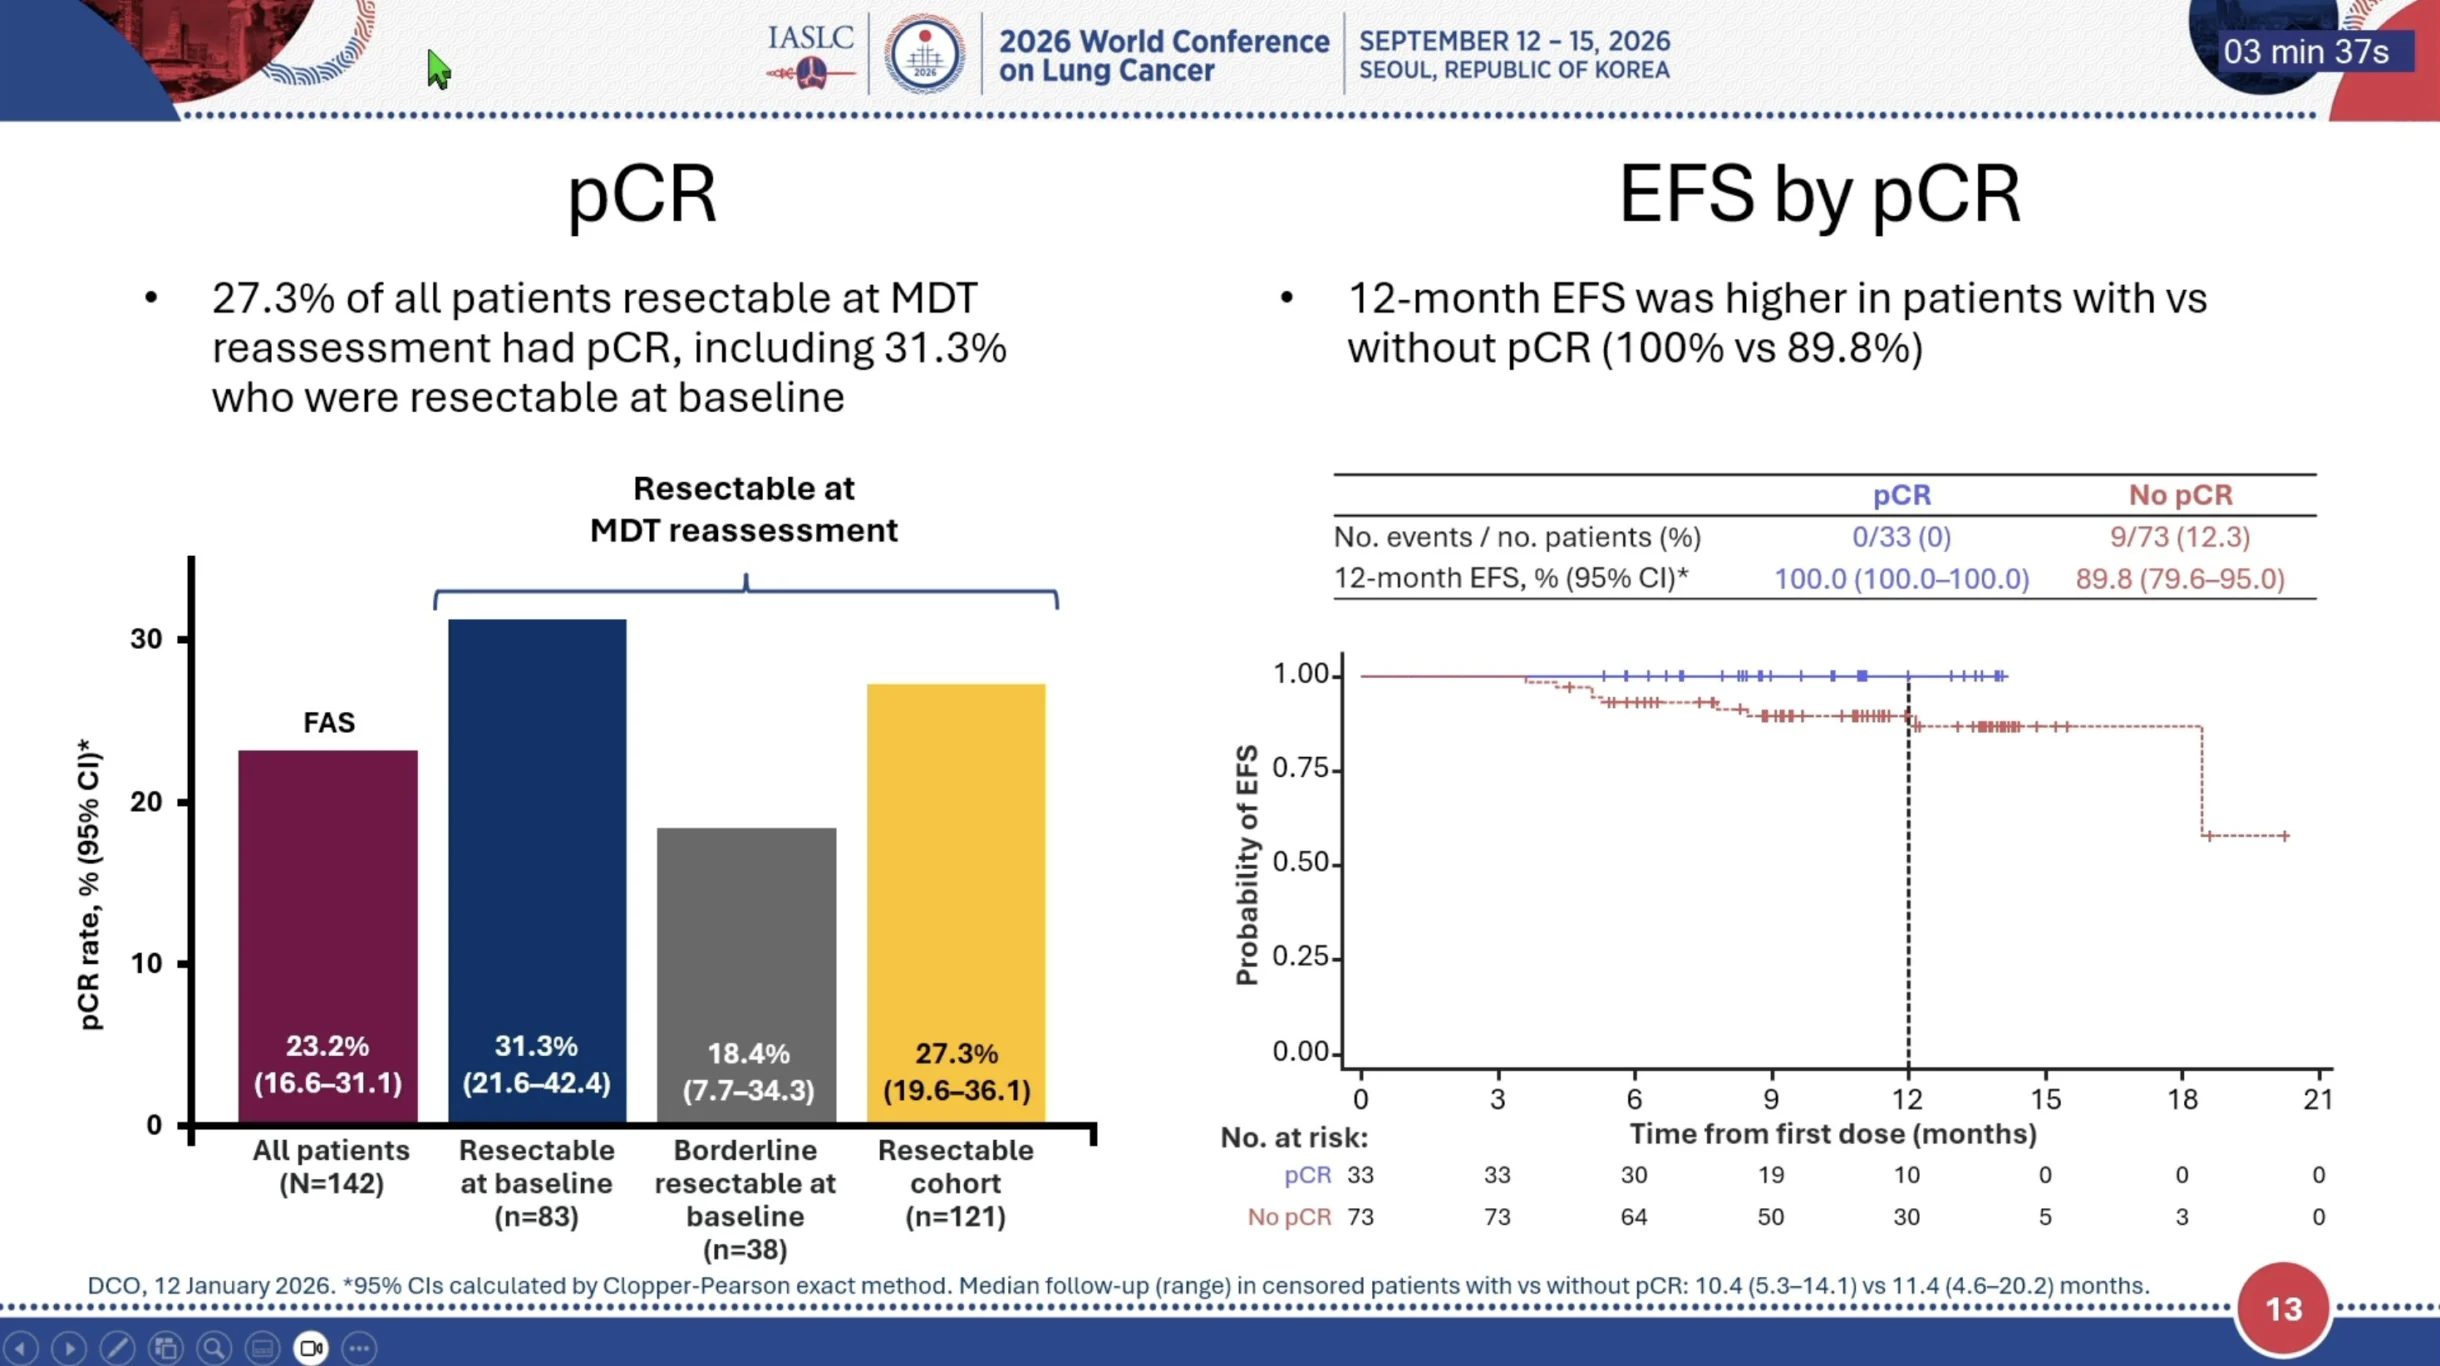
Overall resection rate 75% and 27% pCR rate.”

You can also read: Durvalumab With Radiation Shows Promise in Chemotherapy-Ineligible Locally Advanced NSCLC