Mario Balsa, Medical Oncologist at Hospital Clínic de Barcelona, shared on X:
“ESMO26 | Phase III INTerpath-001
After an early embargo breach, ESMO brought the abstract release forward.
And yes, it’s clearly positive:
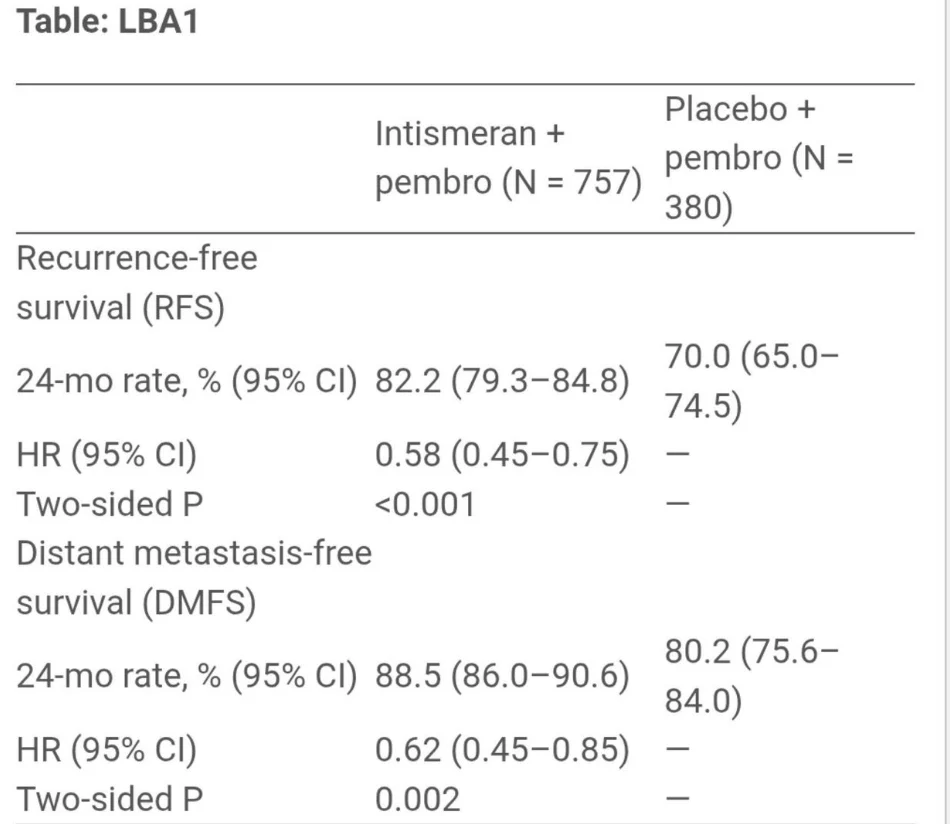
- RFS HR 0.58
- DMFS HR 0.62
But here’s the uncomfortable part: SWOG S1801 also reported an HR 0.58…simply by moving 3 doses of pembrolizumab BEFORE surgery…
Not the same population. Not the same endpoint. Not a cross-trial comparison.
Still, in 2026, should a personalized mRNA vaccine really be benchmarked against adjuvant pembro alone?
Before calling this a new standard, I want to see the vaccine face the Neoadjuvant era. Same HR. Different path. And that may be the real INTerpath question.
Results
1137 pts were randomized: 757 to intismeran + pembro, 380 to placebo + pembro; 726 (95.9%) received ≥1 dose of intismeran and 365 (96.1%) received ≥1 dose of placebo as planned. Median follow-up as of 30Jun2026 was 24.6 mo. Intismeran + pembro significantly improved RFS and DMFS compared with placebo + pembro (Table).
Benefit was similar in stage IIB-IIIB and IIIC-IV MEL and other subgroups. For intismeran + pembro vs placebo + pembro, AEs were grade ≥3 in 23.6% vs 20.3%; 6.5% vs 5.3% discontinued both drugs simultaneously due to an AE. Most common AEs were pyrexia (52.2% vs 8.2%), injection site pain (51.0% vs 9.5%), and fatigue (38.5% vs 29.7%).”