Hamza Hashmi, Myeloma Specialist, Cellular Therapist, and Assistant Attending Physician at Memorial Sloan Kettering Cancer Center, shared on X:
“A few thoughts on CELMoDS as they make their way from appetizers to en·trée on the Myeloma Menu.
Myeloma Menu: Dara-Iber-dex is best suited for pts who are not candidates for CAR-T, BsAb, and CD38 non-refractory at relapse; better non-Heme AE profile than Len and Pom (rash, diarrhea, fatigue).
Positioning the CELMoDs at relapse: IberDd for indolent relapses in the early-relapse setting; mezigdomide based combinations for aggressive relapses and higher-risk biology.
CELMoDS can be very enticing as holding/bridging therapy but cytopenias may affect leukapheresis and manufacturing.
Practical implications:
- Best suited for pts who are not candidates for CAR-T, BsAb, and CD38 non-refractory at relapse; better non-Heme AE profile than Len and Pom
- Oral CELMoD + SC dara, with no twice-weekly bortezomib clinic visits should replace DVd
- Weekly CBCs in cycles 1–2; liberal use of G-CSF and dose holds as Dara dosing becomes less frequent
- Antiviral + antibacterial + VTE prophylaxis recommended given AE profile
- Monitor Age≥75 closely as more AEs; same for Black and t(11:14) as they tend to have more neutropenia
Unanswered questions:
- Where does this fit best as anti-CD38-refractory patients are now the majority in U.S.
- MRD comparison with SOC at 1st relapse i.e. DKd, DPd, CAR-T, bispecifics
- Will PFS and OS confirm the MRD benefit?
- Can prophylaxis lower infections in older patients?
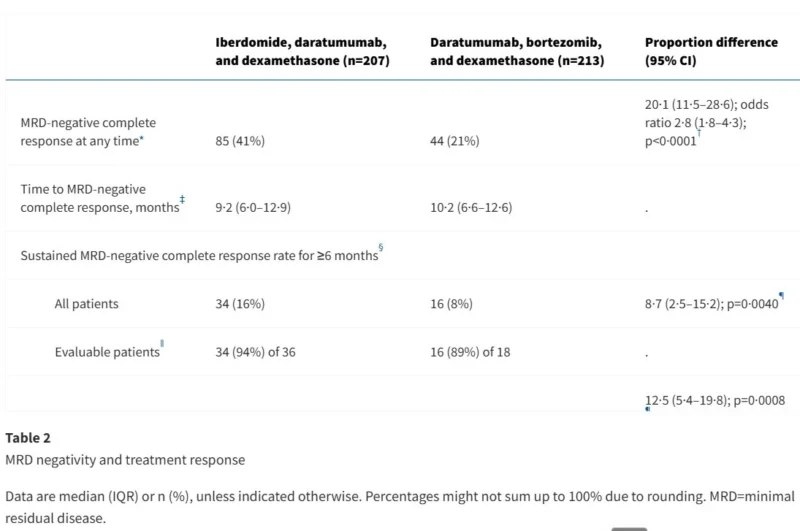
- Quality of life on continuous therapy? In summary, IberDd doubles MRD-neg CR, spares neuropathy, and brings CELMoDs into our clinical practice. The cost is early neutropenia and more infections, so proactive supportive care is essential.”
You can also read: BMS Reports Iberdomide Combination Reduces Risk of Progression or Death by 51% in Relapsed or Refractory Multiple Myeloma