


Binimetinib (Mektovi): Understanding Its Mechanism, Dosing, Clinical Uses, and Role in BRAF V600–Mutated Melanoma and NSCLC
Key takeaways
- Binimetinib is an oral MEK1/MEK2 inhibitor.
- It is FDA approved only in combination with encorafenib.
- Standard dosing is 45 mg orally twice daily, approximately 12 hours apart.
- It may be taken with or without food.
- The first dose reduction is 30 mg twice daily.
- Moderate or severe hepatic impairment also requires 30 mg twice daily. Access Data
- FDA-approved indications include BRAF V600E/K metastatic melanoma and BRAF V600E metastatic NSCLC.
- COLUMBUS showed median PFS 14.9 vs 7.3 months, median OS 33.6 vs 16.9 months, and ORR 63% vs 40% versus vemurafenib.
- At 5 years, OS with encorafenib/binimetinib was 35%.
- PHAROS showed ORR 75% in treatment-naïve and 46% in previously treated BRAF V600E NSCLC.
- Updated PHAROS results showed median PFS 30.2 months and median OS 47.6 months in treatment-naïve patients.
- Important toxicities include cardiomyopathy, VTE, ocular toxicity, ILD, hepatotoxicity, CPK elevation/rhabdomyolysis, and hemorrhage.
- In 2026, binimetinib is best understood as the MEK component of encorafenib-based BRAF/MEK dual blockade.
Binimetinib (Mektovi) is an oral, reversible inhibitor of MEK1 and MEK2, key components of the RAS–RAF–MEK–ERK/MAPK pathway. By suppressing MEK activity, binimetinib reduces downstream ERK phosphorylation and inhibits proliferation and survival signaling in tumors driven by MAPK-pathway activation.
In current practice, binimetinib is FDA approved only in combination with encorafenib for two settings: BRAF V600E- or V600K-mutated unresectable/metastatic melanoma and BRAF V600E-mutated metastatic NSCLC. The standard dose is 45 mg orally twice daily, approximately 12 hours apart, with or without food.
Key Facts
- Generic name: Binimetinib
- Brand name: Mektovi
- Drug class: MEK1/MEK2 inhibitor
- Route: Oral
- Initial US approval: 2018
- Primary targets: MEK1 and MEK2
- Standard dose: 45 mg orally twice daily
- Administration: Approximately 12 hours apart
- Food: With or without food
- Tablet strength: 15 mg
- Combination partner: Encorafenib
- FDA indications: BRAF V600E/K melanoma; BRAF V600E metastatic NSCLC
- First dose reduction: 30 mg twice daily
- Moderate/severe hepatic impairment: 30 mg twice daily
- Important toxicities: Cardiomyopathy, VTE, ocular toxicity, ILD/pneumonitis, hepatotoxicity, CPK elevation/rhabdomyolysis, hemorrhage, new primary malignancies
- Current US status: FDA approved.
What Is Binimetinib?
Binimetinib is a small-molecule inhibitor of:
MEK1 and MEK2
also known as:
MAP2K1 and MAP2K2.
MEK1/2 occupy a central position within the:
RAS → RAF → MEK → ERK
signaling pathway.
This pathway regulates:
- Cell proliferation
- Survival
- Differentiation
- Migration
- Gene transcription
In cancers with activating BRAF V600 mutations, abnormal BRAF activity causes persistent MEK and ERK signaling.
Binimetinib interrupts this pathway downstream of BRAF.
What Is the Mechanism of Action of Binimetinib?
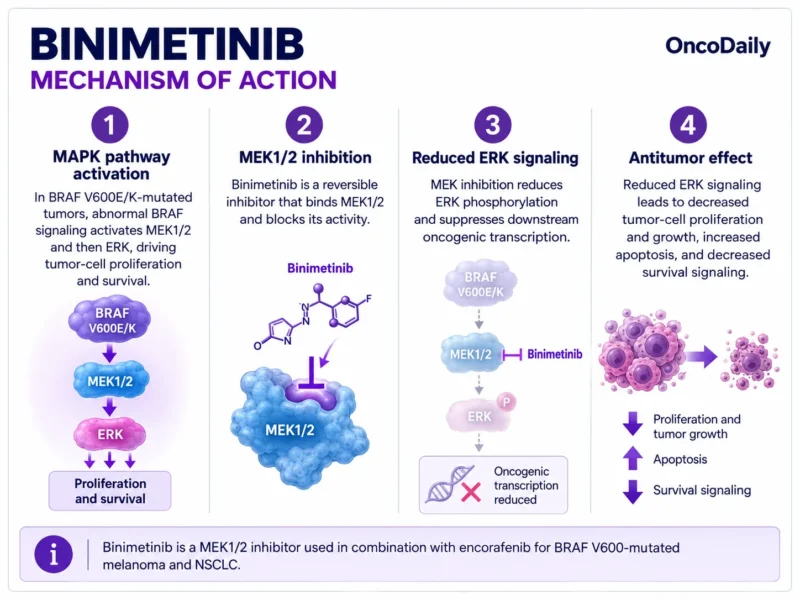
1. BRAF V600 Mutation Activates MAPK Signaling
BRAF V600E or V600K mutations produce constitutively active BRAF kinase.
This continuously activates:
MEK1/2
which then activate:
ERK1/2.
2. Binimetinib Reversibly Inhibits MEK1 and MEK2
Binimetinib is a:
Reversible MEK1/2 inhibitor.
It inhibits both MEK activity and downstream ERK phosphorylation.
3. ERK Signaling Is Reduced
MEK inhibition decreases:
- ERK activation
- MAPK-dependent transcription
- Cell-cycle signaling
- Pro-survival signaling
4. Tumor Proliferation Falls
The result is:
- Reduced proliferation
- Reduced survival
- Increased apoptosis
- Reduced tumor growth
The mechanism can be summarized as:
Binimetinib → MEK1/2 inhibition → reduced ERK phosphorylation → suppression of MAPK signaling → reduced tumor-cell proliferation and survival.
Why Is Binimetinib Combined With Encorafenib?
Encorafenib inhibits:
Mutant BRAF
while binimetinib inhibits:
MEK1/2 downstream of BRAF.
This dual blockade suppresses the pathway at two levels:
BRAF → MEK → ERK.
Compared with BRAF inhibition alone, BRAF/MEK combination therapy can:
- Deepen MAPK-pathway suppression
- Delay resistance
- Improve response durability
- Improve progression-free survival
- Improve overall survival
- Reduce some paradoxical BRAF-inhibitor toxicities
The combination is established in both:
- BRAF V600-mutated melanoma
- BRAF V600E-mutated metastatic NSCLC
What Is the Dose of Binimetinib?
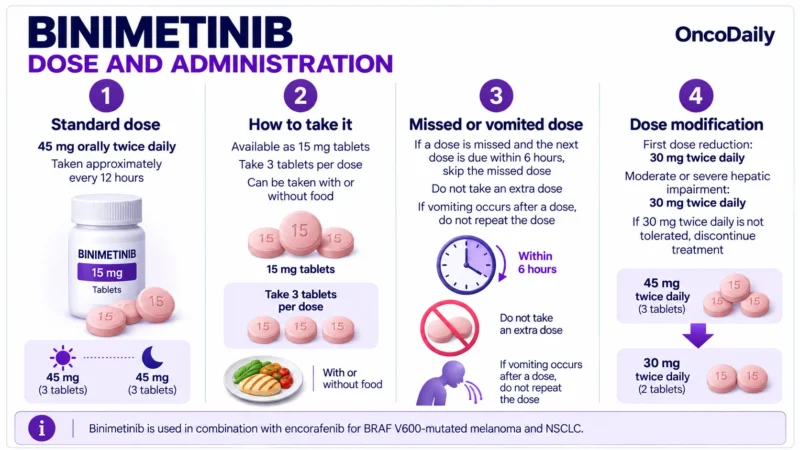
The recommended dose is:
45 mg orally twice daily
approximately:
12 hours apart
in combination with encorafenib.
Treatment continues until:
- Disease progression
- Unacceptable toxicity.
How Is Binimetinib Administered?
Binimetinib is available as:
15 mg tablets.
A 45 mg dose therefore corresponds to:
Three 15 mg tablets per dose.
It may be taken:
With or without food.
The twice-daily doses should be taken approximately:
12 hours apart.
What If a Dose Is Missed?
If a dose is missed:
Do not take the missed dose if the next scheduled dose is due within:
6 hours.
Otherwise, take it when remembered.
If vomiting occurs after administration:
Do not take an additional dose.
Continue with the next scheduled dose.
How Are Binimetinib Dose Reductions Made?
Starting dose:
45 mg twice daily
First dose reduction:
30 mg twice daily.
If the patient cannot tolerate:
30 mg twice daily
binimetinib should generally be:
Permanently discontinued.
If encorafenib is permanently discontinued:
Binimetinib should also be discontinued.
Dose interruption, reduction, or discontinuation may be required for:
- Cardiomyopathy
- Venous thromboembolism
- Serous retinopathy
- Uveitis
- ILD/pneumonitis
- Hepatotoxicity
- CPK elevation
- Rhabdomyolysis
- Hemorrhage
- Severe dermatologic toxicity
What Are the Important Drug Interactions With Binimetinib?
Unlike many oral targeted therapies, the current FDA prescribing information states:
No clinically important drug interactions have been observed with binimetinib.
However, because binimetinib is given with encorafenib, the interaction profile of the full regimen must still be reviewed carefully.
This is especially important because encorafenib has clinically significant:
- CYP3A4 interactions
- Transporter interactions
- QT-related considerations
Therefore, medication review should always consider the combination regimen, not binimetinib in isolation.
Does Binimetinib Require Renal or Hepatic Dose Adjustment?
Renal Impairment
No routine starting-dose adjustment is generally required for mild-to-moderate renal impairment.
Data are more limited in severe renal dysfunction.
Hepatic Impairment
No adjustment is required for:
Mild hepatic impairment.
For:
- Moderate hepatic impairment
- Severe hepatic impairment
the recommended dose is:
30 mg orally twice daily.
What Is the Pharmacokinetic Profile of Binimetinib?
Absorption
Binimetinib exposure is approximately dose proportional.
After twice-daily administration, steady-state accumulation is approximately:
1.5-fold.
Food Effect
Binimetinib may be taken:
With or without food.
No clinically important food restriction is required.
Protein Binding
Binimetinib is approximately:
97% plasma protein bound.
Because of this high protein binding:
Hemodialysis is unlikely to be effective in overdose.
QT Effect
At the approved:
45 mg twice-daily dose
no clinically meaningful QT prolongation was observed.
What Are the Clinical Uses of Binimetinib?
1. BRAF V600E/K-Mutated Unresectable or Metastatic Melanoma
Binimetinib is FDA approved:
In combination with encorafenib
for patients with unresectable or metastatic melanoma harboring:
- BRAF V600E
- BRAF V600K
mutations.
2. BRAF V600E-Mutated Metastatic NSCLC
Binimetinib is also FDA approved:
In combination with encorafenib
for adults with metastatic NSCLC harboring:
BRAF V600E.
What Did Binimetinib Clinical Trials Show?
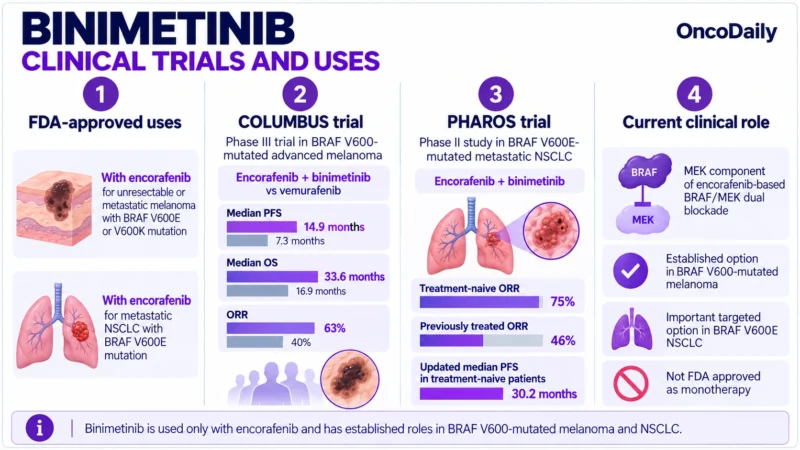
COLUMBUS — BRAF V600-Mutated Melanoma
The pivotal phase III COLUMBUS trial evaluated:
Encorafenib + binimetinib
versus:
Vemurafenib
and encorafenib monotherapy in advanced BRAF V600-mutated melanoma.
A total of:
577 patients
were randomized.
Among the approved-regimen comparison:
- Encorafenib + binimetinib: 192
- Vemurafenib: 191.
Median Progression-Free Survival
- Encorafenib + binimetinib: 14.9 months
- Vemurafenib: 7.3 months
Hazard ratio:
0.54
P < 0.0001.
Median Overall Survival
- 33.6 months
- 16.9 months
respectively.
Hazard ratio:
0.67.
Objective Response Rate
- 63% with encorafenib + binimetinib
- 40% with vemurafenib
Complete responses occurred in:
- 8%
- 6%
respectively.
Median Duration of Response
- 16.6 months
- 12.3 months
respectively.
COLUMBUS — 5-Year Outcomes
At 5 years:
Progression-Free Survival
- 23% with encorafenib + binimetinib
- 10% with vemurafenib
Overall Survival
- 35%
- 21%
respectively.
Among patients with normal LDH at baseline:
- 5-year PFS: 31%
- 5-year OS: 45%.
These results support durable long-term benefit from dual BRAF/MEK blockade.
PHAROS — BRAF V600E-Mutated Metastatic NSCLC
The phase II PHAROS study evaluated:
Encorafenib 450 mg once daily + binimetinib 45 mg twice daily
in patients with BRAF V600E-mutated metastatic NSCLC.
The efficacy population included:
- 59 treatment-naïve patients
- 39 previously treated patients.
PHAROS — Treatment-Naïve Patients
Objective Response Rate
75%.
Complete response:
15%.
Partial response:
59%.
Duration of Response
Among responders:
- 64% had DoR ≥12 months
- 43% had DoR ≥24 months.
With longer follow-up:
Median Duration of Response
40.0 months.
Median Progression-Free Survival
30.2 months.
Median Overall Survival
Updated analysis:
47.6 months.
4-Year Overall Survival Probability
49%.
PHAROS — Previously Treated Patients
Objective Response Rate
46%.
Complete response:
10%.
Partial response:
36%.
With longer follow-up:
Median Duration of Response
16.7 months.
Median Progression-Free Survival
9.3 months.
Median Overall Survival
22.7 months.
4-Year Overall Survival Probability
31%.
What About Brain Metastases?
In COLUMBUS:
Approximately:
3%
of patients had baseline brain metastases.
In PHAROS:
Approximately:
8%
had brain metastases at baseline.
These trials were not dedicated intracranial-efficacy studies, so the evidence base for CNS-specific activity is smaller than for some modern EGFR or ALK inhibitors.
Nevertheless, encorafenib plus binimetinib is used as systemic targeted therapy in BRAF V600-driven melanoma and NSCLC, including selected patients with CNS disease.
What About NRAS-Mutant Melanoma?
Binimetinib was also studied as monotherapy in:
NRAS-mutated advanced melanoma
in the phase III:
NEMO trial.
A total of:
402 patients
were randomized to:
- Binimetinib 45 mg twice daily
- Dacarbazine.
Median PFS
- 2.8 months with binimetinib
- 1.5 months with dacarbazine
Hazard ratio:
0.62
P < 0.001.
However, the benefit was modest and did not establish binimetinib monotherapy as an FDA-approved treatment for NRAS-mutant melanoma.
Therefore:
NRAS-mutant melanoma is not a current FDA-approved indication for binimetinib.
Is Binimetinib FDA Approved?
Yes.
Binimetinib received its initial US approval in:
2018.
Its FDA-approved uses are:
Melanoma
With encorafenib for BRAF V600E/K-mutated unresectable or metastatic melanoma.
NSCLC
With encorafenib for BRAF V600E-mutated metastatic NSCLC.
What Is the Current Clinical Role of Binimetinib?
Melanoma
Binimetinib is used as part of:
Encorafenib + binimetinib
for BRAF V600E/K-mutated advanced melanoma.
The combination is one of several established BRAF/MEK regimens, alongside:
- Dabrafenib + trametinib
- Vemurafenib + cobimetinib
Treatment selection depends on:
- Prior immunotherapy
- Disease burden
- CNS disease
- LDH
- Toxicity profile
- Need for rapid disease control
- Patient preference and access
NSCLC
Binimetinib now has an important role in:
BRAF V600E-mutated metastatic NSCLC
through the:
Encorafenib + binimetinib
combination.
PHAROS demonstrated particularly durable outcomes in treatment-naïve patients, with updated median PFS of:
30.2 months
and median OS of:
47.6 months.
Read more: OncoDaily’s coverage of the updated overall survival results from the PHAROS study, evaluating encorafenib + binimetinib in BRAF V600E-mutant metastatic NSCLC.
Watch more: Explore OncoDaily’s discussion on BRAF V600E-mutated NSCLC and the evolving role of targeted therapy with BRAF/MEK inhibition.
What Are the Major Side Effects of Binimetinib?
Common adverse effects when combined with encorafenib include:
Melanoma
- Fatigue
- Nausea
- Diarrhea
- Vomiting
- Abdominal pain.
NSCLC
Common adverse reactions include:
- Fatigue
- Nausea
- Diarrhea
- Musculoskeletal pain
- Vomiting
- Abdominal pain
- Visual impairment
- Constipation
- Dyspnea
- Rash
Cough.
Cardiomyopathy
Binimetinib can cause:
Left ventricular dysfunction and cardiomyopathy.
In COLUMBUS:
Cardiomyopathy occurred in approximately:
7%.
In PHAROS:
Approximately:
11%.
LVEF should be assessed:
- Before treatment
- After approximately 1 month
- Every 2–3 months thereafter.
Venous Thromboembolism
Binimetinib plus encorafenib can cause:
- Deep-vein thrombosis
- Pulmonary embolism
VTE occurred in:
- 6% in COLUMBUS
- 7% in PHAROS.
Patients should be evaluated urgently for:
- Leg swelling
- Leg pain
- Sudden dyspnea
- Chest pain
Ocular Toxicity
MEK inhibitors can cause characteristic retinal toxicity.
Important events include:
- Serous retinopathy
- Retinal detachment
- Macular edema
- Retinal vein occlusion
- Uveitis
In COLUMBUS:
Serous retinopathy occurred in approximately:
20%.
Patients should be assessed for visual symptoms:
At each visit.
Ophthalmologic examination is recommended:
- At regular intervals
- For new visual symptoms
- For persistent abnormalities.
Documented retinal vein occlusion requires:
Permanent discontinuation.
Interstitial Lung Disease/Pneumonitis
ILD/pneumonitis is uncommon but potentially serious.
Patients should be assessed for:
- New cough
- Dyspnea
- Hypoxia
- New pulmonary findings
Grade 3 or 4 ILD generally requires:
Permanent discontinuation.
Hepatotoxicity
Binimetinib can cause elevations in:
- ALT
- AST
- Alkaline phosphatase
- Bilirubin
Liver function tests should be checked:
- Before treatment
- Monthly during treatment
- As clinically indicated.
Rhabdomyolysis and CPK Elevation
CPK elevation is relatively common.
In COLUMBUS:
58%
had elevated CPK.
In PHAROS:
41%
had elevated CK.
Monitoring should include:
- CPK
- Creatinine
- Muscle symptoms
before therapy and periodically during treatment.
Hemorrhage
Hemorrhagic events may occur with the combination.
In COLUMBUS:
- Any-grade hemorrhage: 19%
- Grade ≥3 hemorrhage: 3.2%.
In PHAROS:
- Hemorrhage: 12%
- Grade 3–4 hemorrhage: 4.1%.
Patients should be monitored for:
- GI bleeding
- Intracranial bleeding
- Other clinically significant hemorrhage
New Primary Malignancies
New cutaneous and noncutaneous malignancies can occur when binimetinib is administered with encorafenib.
Patients should be monitored:
- Before therapy
- During therapy
- After treatment discontinuation.
Embryo-Fetal Toxicity
Binimetinib can cause fetal harm.
Females of reproductive potential should use:
Effective contraception
during treatment and for:
30 days after the final dose.
Breastfeeding is not recommended:
- During treatment
- For 3 days after the last dose.
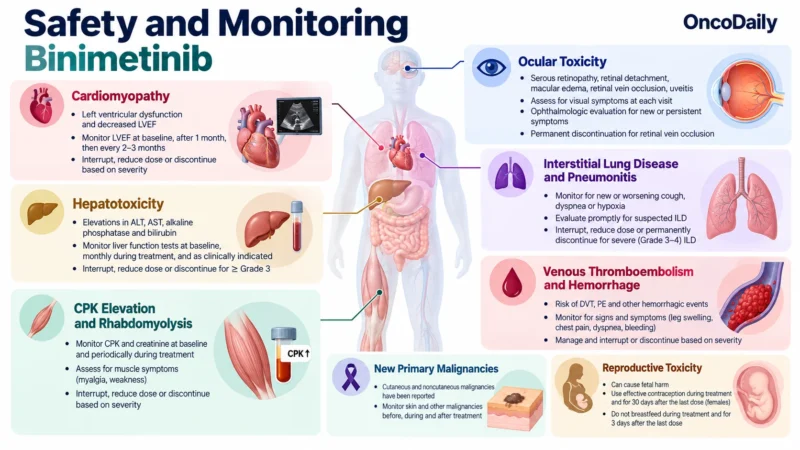
What Monitoring Is Required?
Monitoring during binimetinib therapy should include:
- Confirm BRAF mutation before treatment
- LVEF before treatment
- LVEF after 1 month
- LVEF every 2–3 months
- Signs of DVT/PE
- Visual symptoms at each visit
- Ophthalmologic evaluation
- Respiratory symptoms
- ALT
- AST
- Bilirubin
- Liver tests monthly
- CPK
- Creatinine
- Muscle symptoms
- Signs of hemorrhage
- Skin and other new malignancies
- Pregnancy counseling
- Particular attention should be given to:
Cardiac function, retinal toxicity, VTE, pulmonary symptoms, liver function, muscle toxicity, and bleeding.
FAQ
What Is Binimetinib Used For?
- BRAF V600E/K-mutated metastatic melanoma
- BRAF V600E-mutated metastatic NSCLC
What Is the Standard Dose?
Can Binimetinib Be Taken With Food?
It can be taken:
With or without food.
What Is the First Dose Reduction?
How Does Binimetinib Work?
Why Is Binimetinib Combined With Encorafenib?
What Did COLUMBUS Show?
- 14.9 months with encorafenib + binimetinib
- 7.3 months with vemurafenib.
What Did PHAROS Show?
- ORR: 75%
- Median DoR: 40.0 months
- Median PFS: 30.2 months
- Median OS: 47.6 months. PubMed
Is Binimetinib FDA Approved for NRAS-Mutant Melanoma?
NEMO demonstrated a modest PFS benefit, but this did not lead to an FDA-approved NRAS melanoma indication. PubMed
What Are the Most Important Safety Concerns?
Cardiomyopathy, VTE, retinal toxicity, ILD/pneumonitis, hepatotoxicity, rhabdomyolysis, and hemorrhage.