



Tobias Büttner, Board-certified Urologist, shared Tyler Seibert’s, Associate Professor in the Division of Radiation Oncology at UCSD and a member of the RMAS Center for Precision Radiation Medicine (CPRM), post on X, adding:
“Great trial!
Another strength of imaging might be shortening ADT.
I doubt the ADT/RT synergy for true eradication lasts as long as our trial-based durations.
Later on, ADT mostly buys suppression, and may favor resistant clones.
Worth 18-36 mo vs. a sequenced approach?
My impression is that fear of masked progression bothers us doctors more than our patients.
After RT, most hand follow-up over to us. After RP, they grow into the PSA thing, mostly because they notice how much I care about that number.
What they feel every day is the ADT.
Would a recurrence growing on mpMRI under ADT also light up on PSMA PET?
If yes: miN0 miM0 → 18 mo ADT → PSMA PET after T recovery, regardless of PSA.
Worth testing prospectively?”
Quoting Tyler Seibert’s post:
“ARIEL trial: Paper and thread on MRI changes with RT+ADT for Prostate Cancer.
At some point during/after prostate RT, every patient asks:
Can you tell if it is working?
PSA is great. But we have to wait a long time for T recovery.
Most wish we could *look* to see what happens to the cancer. So, we conducted a trial with serial MRI.

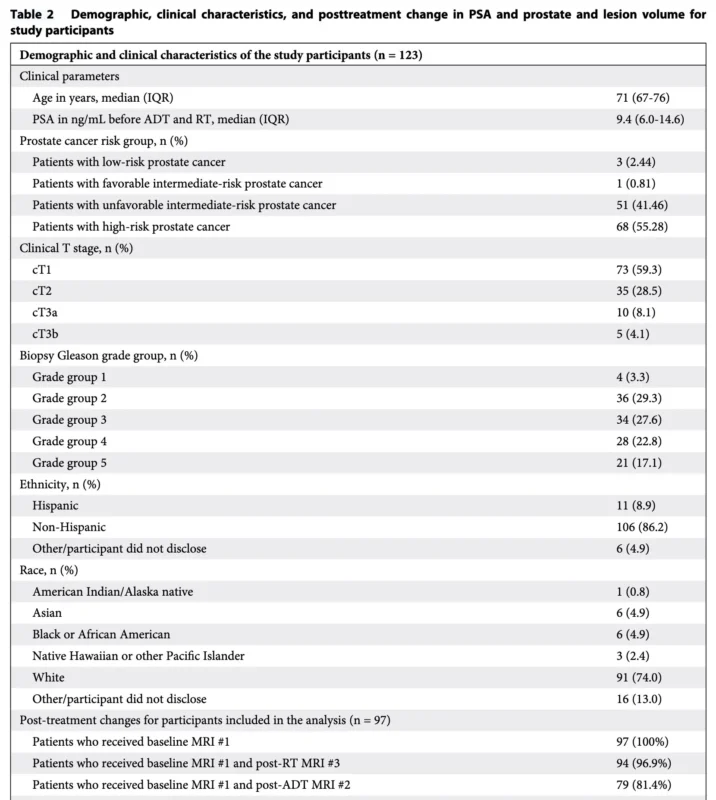
Key eligibility: Unfav int- or high-risk prostate cancer, planning RT+ADT.
MRI No. 2 was optional if no neoadjuvant ADT or logistically difficult for patient
Some patients dropped out (e.g., declined ADT, started ADT before MRI, etc.)
N=94 analyzable.
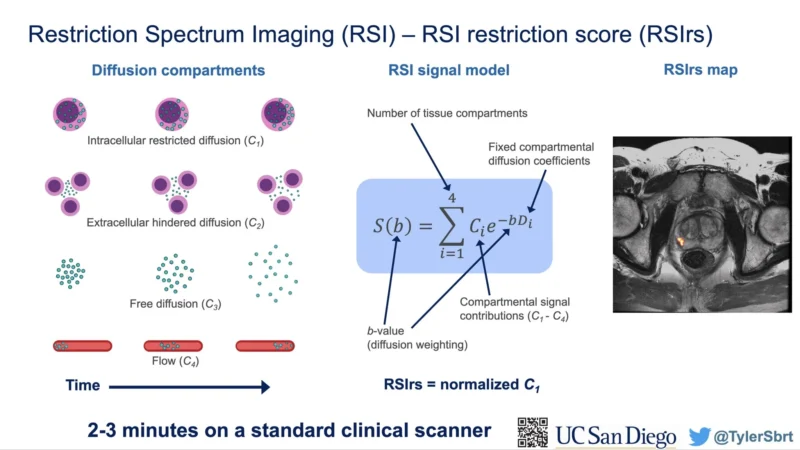
Each MRI was mp or bp, plus RSI. The RSI restriction score (RSIrs) is a quantitative biomarker based on advanced diffusion MRI sequences.
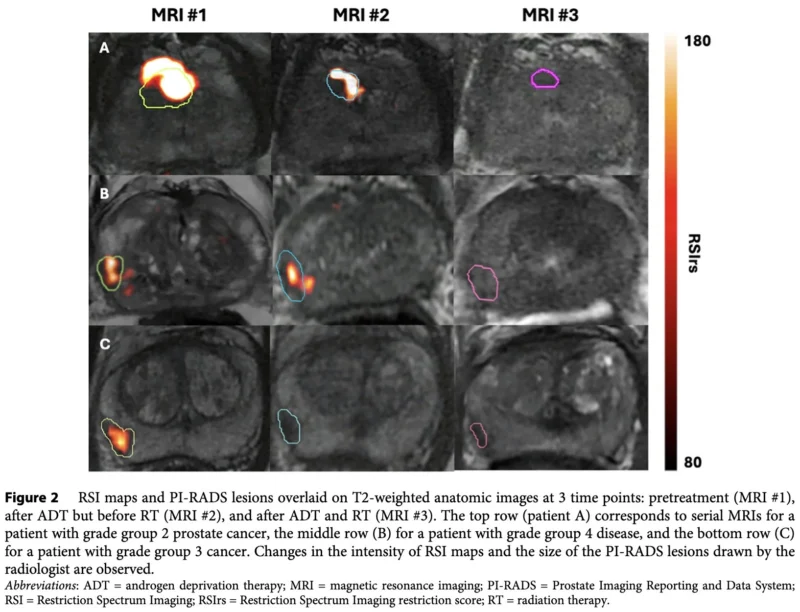
From pre-treatment to post-RT:
- Prostate volume down by approximately by 37%
- Tumor volume down by approximately by 77% ‼
Only 60% of lesions still visible at MRI No. 2.
Only 9% visible at MRI No. 3 – maybe good?
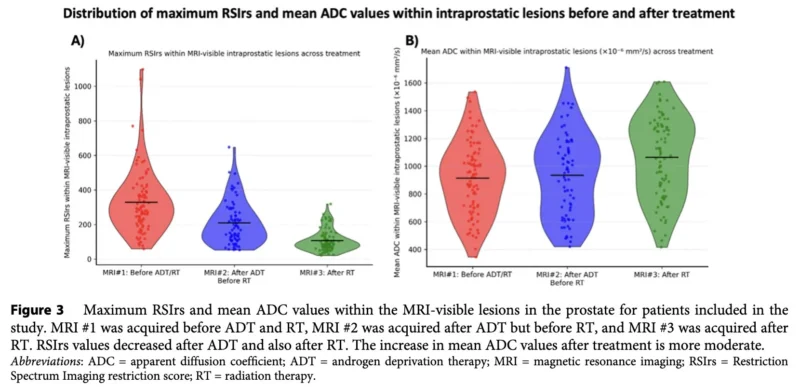
Negative Mean ADC in lesion increases with treatment, but not consistent.
Maximum RSIrs in lesion generally decreases with treatment
Can this be an indicator of treatment response?
Changes for each patient’s lesion:
Positive: RSIrs mostly well behaved: Decreases with treatment. A few increase pre-ADT, then decrease – maybe testosterone flare?
Negative: ADC more chaotic.
Will early MRI response predict long-term outcomes? Time will tell.
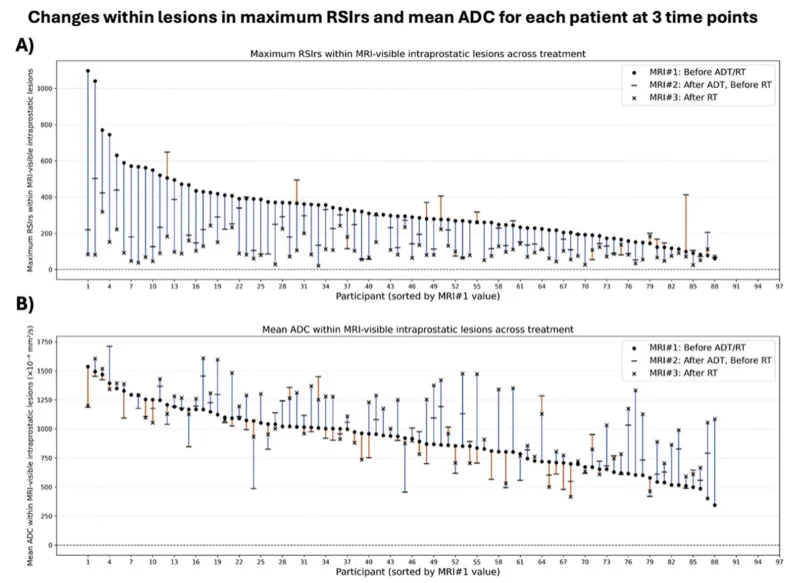
Some lessons from ARIEL serial MRI trial for those offering focal boost to prostate cancer.

Thanks to patients who got in the MRI tube for research
Thanks to physicians who enrolled patients
Thanks to research team for consenting and collecting data
And thanks to ASTRO and PCF Science for funding the trial.”
Title: Androgen Deprivation Therapy (ADT) and Radiotherapy (RT) with Imaging Evaluation Longitudinally (ARIEL) trial: protocol, early results, and implications of neoadjuvant ADT for focal RT boost in prostate cancer
Authors: Yuze Song, Mariluz Rojo Domingo, Lily Nguyen, Christopher C Conlin, Nitin Dhillon, Son Do, Anna Dornisch, Michael E Hahn, Roshan Karunamuni, Joshua Kim, Kang-Lung Lee, Jasmine Liu, Rana R McKay, Loren K Mell, Arno J Mundt, Rakesh Patel, Edmund M Qiao, Brent Rose, Rhea Rupareliya, Hadley Schaub, Armin Schwartzman, Tyler Stewart, Anders M Dale, Tyler M Seibert ARIEL investigators
You can also read:
Bishal Gyawali: Letter to the Editor and Author Response on the ARIEL-4 Trial
